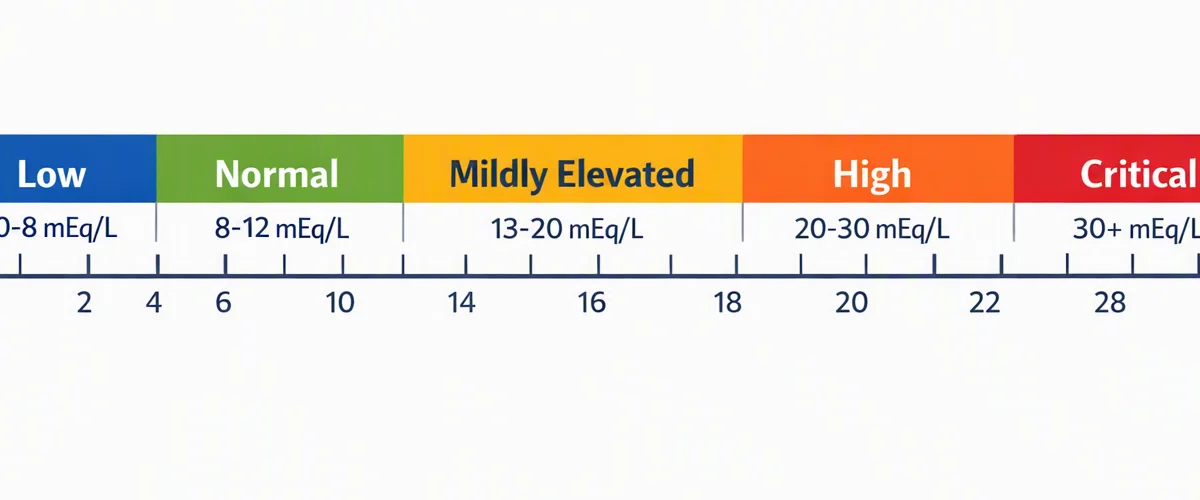
What a high anion gap means
The anion gap is a helpful way to evaluate serum chemistry and identify an acid-base disorder. A high anion gap usually points to anion gap metabolic acidosis, which develops when acid builds up in the body or when normal base is lost. Put simply, the gap rises because of extra unmeasured anions in the blood.

This pattern matters because it narrows the differential diagnosis. Instead of looking only at pH, clinicians use the gap as a biochemical marker of acid buildup and possible acid accumulation. A high result can reflect metabolic acidosis from nonserious causes, but it can also be the first sign of poisoning or another dangerous metabolic derangement.
The concept is closely tied to acid-base balance. When the body produces or absorbs acids faster than it can clear them, bicarbonate is consumed and the gap often rises. This is why a high result is not a diagnosis by itself; it is a clue that guides the next step in the diagnostic workup.
How an Anion Gap Calculator is used
An Anion Gap Calculator is a quick way to approximate the gap from routine lab values. It uses serum sodium, serum chloride, and serum bicarbonate to apply the anion gap formula. In its usual form, it helps clinicians spot a lab abnormality that may not be clear from symptoms alone.
This tool aids laboratory interpretation during rapid assessment. If the gap is elevated, the result can indicate a hidden acid load and trigger a broader search for the cause. That search often includes checking for toxic ingestion, reviewing medications, and assessing for other conditions that lead to acid buildup.
The calculator is especially useful when the clinical presentation is unclear. A patient may have nausea, confusion, shortness of breath, or appear generally ill. The calculator can turn a vague concern into a clearer plan by identifying whether the issue fits a high-gap acid-base disorder.
Although the number is significant, it should always be interpreted together with the rest of the evaluation. A normal or abnormal result does not exist alone. It must be paired with the history, exam, and related tests such as blood gas analysis and toxin screening when indicated.
Toxins that lead to a high anion gap
Several toxins can cause a high anion gap by causing generalized acid buildup. The main concerns are ethylene glycol, methanol, salicylates, and propylene glycol. These exposures are significant because they may progress quickly and because early treatment can prevent serious injury.
These substances are often discussed under the category of toxic alcohols, though not all of them are alcohols in the everyday sense. Some are used as solvents, some are drugs, and some are byproducts that create an acid load after they are broken down by the body. The common result is anion gap metabolic acidosis from accumulating acids.
Ethylene glycol is commonly linked to antifreeze exposure. It is metabolized into acidic compounds that elevate the anion gap and can damage the kidneys. Methanol is another major toxic alcohol; it is dangerous because its metabolites can damage the optic system and create significant acidosis. Both are medical emergencies.
Salicylates, including aspirin overdose, can also elevate the gap. They often create a mixed picture with more than one acid-base abnormality, which can make interpretation more difficult. Propylene glycol can be seen as a vehicle in some medications and infusions, and in high amounts it may also contribute to acidosis and a increasing gap.
Toxic ingestions related to alcohols
Alcohol-related toxic ingestions are among the key causes to consider when the osmolar gap and anion gap are both abnormal. Methanol and ethylene glycol are the classic examples. Early after exposure, the osmolar gap may be high because the parent compound is still present. Later, as metabolism proceeds, the anion gap may rise as acidic metabolites build up.
This timing plays a role. A patient may present with a normal or only mildly elevated gap early on, then develop a dramatic increase later. That is why clinicians rely on ongoing assessment, not a single value. The pattern can help differentiate a toxic alcohol exposure from other forms of metabolic acidosis.
Methanol poisoning often leads to visual disturbances, while ethylene glycol more often causes kidney injury and crystals in the urine. In both situations, the acid-base pattern reflects the same underlying problem: the body is converting a poison into acids more quickly than it can remove them.
Medication and chemical causes
Not every toxin-related high gap comes from drinking a toxic alcohol. Salicylates are a major medication cause and can lead to an elevated gap through several mechanisms, including increased acid production and altered metabolism. A person with salicylate toxicity may also show respiratory findings that make the picture more complex.
Propylene glycol is another important chemical cause. It may be found in some IV medications or preparations, and large exposures can cause a clinically significant acid-base disturbance. Although less familiar than methanol or ethylene glycol, it belongs in the workup when an unexplained gap is identified in a hospitalized patient.
Isoniazid is also clinically relevant. Overdose can produce severe neurologic toxicity and metabolic complications, sometimes including acidosis. Because the presentation may evolve quickly, it should remain on the list when the history suggests possible medication ingestion.
Other serious causes of elevated anion gap acidosis
Poisons are only one part of the clinical differential. Various non-toxic disorders also cause high anion gap conditions, and they can appear alike on first assessment. Most significant include lactic acidosis, ketoacidosis, and renal failure.

Lactic acidosis develops when tissues are poorly perfused, oxygen delivery is impaired, or metabolism is altered. It is a frequent cause of metabolic acidosis and can appear in shock, severe infection, seizures, or other conditions that produce widespread physiologic stress. Because lactate is an unmeasured anion, it contributes directly to the gap.
Ketoacidosis is another frequent cause. It can arise in diabetes, alcohol use, or prolonged fasting. Ketone bodies act as unmeasured anions, generating the same pattern of anion gap metabolic acidosis. The history often gives away the diagnosis, but the lab pattern confirms the concern.
Renal failure causes the kidneys to accumulate acids and be unable to clear normal metabolic byproducts. Over time, this causes accumulation of unmeasured acids and a progressively increasing gap. In a patient with chronic kidney disease or acute kidney injury, this can resemble toxin-related illness and should be considered carefully.
How clinicians separate toxin exposure from other causes
Differentiating toxic ingestion from other possibilities demands a structured diagnostic workup. The first clues often come from the osmolar gap, an arterial blood gas, and the lactate level. In combination, these help clarify whether the problem is a toxic alcohol, lactic acidosis, ketoacidosis, or a different source of acid-base disturbance.
This gap is especially informative early in toxic alcohol exposure. A high osmolar gap suggests extra low-molecular-weight substances in the blood, such as methanol or ethylene glycol. As metabolism proceeds, the osmolar gap may fall while the anion gap rises. This evolving pattern is a classic clue in laboratory interpretation.
An arterial blood gas helps define the severity of the acidosis and https://anion-gap-estimator566.rivetgarden.com/posts/how-chloride-alters-the-anion-gap shows whether respiratory compensation is present. A patient may hyperventilate to compensate for metabolic acidosis, lowering carbon dioxide and partially balancing the pH. If compensation is inadequate or the patient is tiring, the risk increases.
Lactate testing helps differentiate lactic acidosis from toxin-related causes. A very high lactate may explain the gap, but a normal or only mildly elevated lactate should lead clinicians to consider more strongly toxic alcohols, salicylates, ketoacidosis, or renal failure. The full pattern matters more than any single result.
Symptoms suggesting a toxic ingestion
The clinical presentation of toxin-related acidosis can be wide-ranging and nonspecific, but certain symptoms warrant attention. Mental status changes is a major warning sign, especially if it appears with a high anion gap and no clear alternative explanation. Mental confusion, lethargy, agitation, or decreased responsiveness may all occur.
Visual disturbances are particularly concerning in methanol exposure. Patients may describe blurred vision, decreased acuity, or even the feeling that they are “going blind.” This finding should prompt prompt evaluation for toxic alcohol exposure, even before confirmatory testing returns.
Rapid breathing is another important clue. It often reflects respiratory compensation for metabolic acidosis, as the body tries to blow off carbon dioxide. A fast breathing rate may be one of the earliest visible signs that an acid-base disorder is becoming severe.
Other findings can include nausea, vomiting, abdominal pain, fatigue, or collapse. Because these symptoms overlap with many illnesses, the lab pattern is essential. When symptoms and labs align, the suspicion for a dangerous ingestion increases significantly.
When a high anion gap is a medical emergency
An elevated gap is an emergency when it suggests poisoning, severe metabolic acidosis, or swiftly worsening systemic illness. This is especially true when toxic alcohol exposure is possible, because delays in emergency treatment can lead to blindness, kidney injury, neurologic damage, or death.
Urgent evaluation is also warranted if the patient has altered mental status, severe tachypnea, a rapidly rising gap, or evidence of end-organ injury. In this setting, clinicians may contact poison control, consult toxicology, and begin treatment before all confirmatory studies are back.
Management depends on the cause, but early action can be lifesaving. That may include antidotal therapy, correction of acid-base abnormalities, and sometimes dialysis for severe toxic alcohol exposure or profound acidosis. The key point is that a high gap is not just a lab abnormality; it may be a sign of ongoing systemic toxicity.
Any patient with suspected ingestion, especially of toxic alcohols, should be treated as needing urgent evaluation. The combination of a high anion gap, an abnormal osmolar gap, and concerning symptoms should trigger immediate escalation.
Common questions about toxins and high anion gap
What toxic substances commonly lead to a high anion gap?
The leading toxin-related causes are methanol, ethylene glycol, salicylates, and propylene glycol. These exposures can create anion gap metabolic acidosis by generating acidic metabolites or altering metabolic pathways. In real-world evaluation, toxic alcohols are among the highest-priority causes to rule out.
How does an Anion Gap Calculator help identify toxic ingestions?
An Anion Gap Calculator efficiently determines the gap from serum sodium, serum chloride, and serum bicarbonate. If the result is high, it raises concern for possible hidden acid accumulation and assists in narrowing the differential diagnosis. That makes it valuable when evaluating a possible toxic ingestion or other acid-base disorder.
What is the difference between a high anion gap and an osmolar gap?
The anion gap reflects unmeasured acids in the blood, while the osmolar gap reflects extra dissolved particles that are not accounted for in routine calculations. Toxic alcohols can elevate both, but often at different times during metabolism. A high osmolar gap can suggest recent exposure, while a high anion gap suggests acid-forming metabolites have accumulated.
Do aspirin or salicylates produce a high anion gap?
Yes. Salicylates can cause a high anion gap and may also produce a mixed acid-base picture. They are an important cause of metabolic acidosis and should be considered when the history suggests medication overdose or when the clinical presentation includes ringing in the ears, hyperventilation, or confusion.
When should a high anion gap be treated as a medical emergency?
A high anion gap should be treated as an emergency when there is concern for poisoning, severe symptoms, or rapidly worsening acidosis. Signs such as altered mental status, visual disturbances, tachypnea, or a markedly abnormal arterial blood gas warrant urgent evaluation. If toxic alcohol exposure is possible, immediate toxicology-guided treatment may be needed.