What Is the Anion Gap?
The anion gap is a derived value that helps clinicians evaluate electrolytes and evaluate acid-base balance. It is not actually a lab test by itself. Instead, it is a diagnostic aid derived from routine blood test results, usually from a standard serum chemistry or electrolyte panel.
At its core, the anion gap approximates the difference between the major measured positive and negative ions in the blood. Because some ions are not directly measured, the result can offer clues about anion concentration and the presence of unmeasured anions. That makes it especially helpful in the evaluation of an acid-base disorder, particularly when metabolic acidosis is suspected.
An anion gap calculator is simply a medical calculator that does this calculation for you once the relevant lab values are entered. The result can help with clinical interpretation, but it should always be considered alongside symptoms, the full metabolic panel, and other laboratory findings.
Which Lab Values Does an Anion Gap Calculator Need?
In order to calculate the anion gap, an anion gap calculator typically needs three core lab values: sodium, chloride, and bicarbonate. These values are usually reported as serum sodium, serum chloride, and serum bicarbonate on a serum chemistry report.
These values come from routine blood chemistry testing and are often included in a basic metabolic panel or comprehensive metabolic panel. Most of the time, the calculator uses the same numbers you would see on the lab report, so there is no extra test beyond the standard blood draw.

The contribution of each input is as follows:
- Sodium: the primary measured cation used in the calculation. Chloride: the main measured anion that is subtracted from sodium. Bicarbonate: a central buffer that reflects acid-base status and is also subtracted in the standard formula.
Because these are common measurements in a metabolic panel, the anion gap is easy to compute from everyday laboratory data. In practical terms, the calculator uses the values already available from a routine blood test, which makes it an efficient way to assess electrolyte balance and possible disturbances in acid-base physiology.
How the anion gap formula functions
The usual anion gap formula is:
Anion gap = Sodium - (Chloride + Bicarbonate)This calculated result relies on the measured ions present in the blood, usually expressed in mEq/L. The formula illustrates the fact that the body preserves electrical neutrality, meaning positively charged and negatively charged substances must offset each other. However, not all ions are tested in routine testing.
That is why the anion gap is helpful. It assists estimating the amount of electrically charged ions not directly covered in the basic lab set. These hidden components are often referred to as unmeasured anions. When the gap shifts, it can indicate that something is affecting acid-base physiology or changing the equilibrium of measured and unmeasured substances.
A calculator makes this more straightforward by handling the arithmetic immediately. Still, understanding the calculation formula matters because the result depends entirely on the accuracy of the input values. If the sodium level, chloride level, or bicarbonate level is incorrect, the anion gap will also be inaccurate.
Some clinicians also apply a modified version of the formula that includes potassium, but the standard approach does not require it. The basic version is the one most frequently used in routine clinical interpretation.
Reasons Why Albumin May Play a Role in Clinical Interpretation
While albumin is not part of the standard anion gap formula, it can significantly affect how the result is interpreted. Albumin is a negatively charged protein and a major contributor to the body’s overall electrical balance. When albumin is low, the anion gap may appear lower than expected even if a clinically important acid-base issue is present.
That is why hypoalbuminemia matters. If albumin is reduced, the measured anion gap can underestimate the true burden of unmeasured acids. In that situation, clinicians may calculate an albumin-corrected anion gap to get a better estimate of the underlying problem.
The correction is not always required, but it becomes more relevant when the patient has low protein levels, liver disease, malnutrition, inflammation, or critical illness. In those cases, the usual normal range may not show the full story.
For that reason, albumin is an important part of clinical interpretation even though it is not one of the three core inputs used by most anion gap calculators. A more complete assessment often includes the lab context, the overall electrolyte balance, and whether the patient may have a masked high anion gap due to low albumin.
Which Results Are Considered Normal or Abnormal
The normal anion gap varies somewhat with the laboratory as well as the analyzer used, so the normal range can vary. Several labs list a typical range that is narrow enough to guide interpretation but still somewhat https://anion-gap-widget025.tearosediner.net/anion-gap-calculator-how-to-determine-acid-base-status different from one system to another.
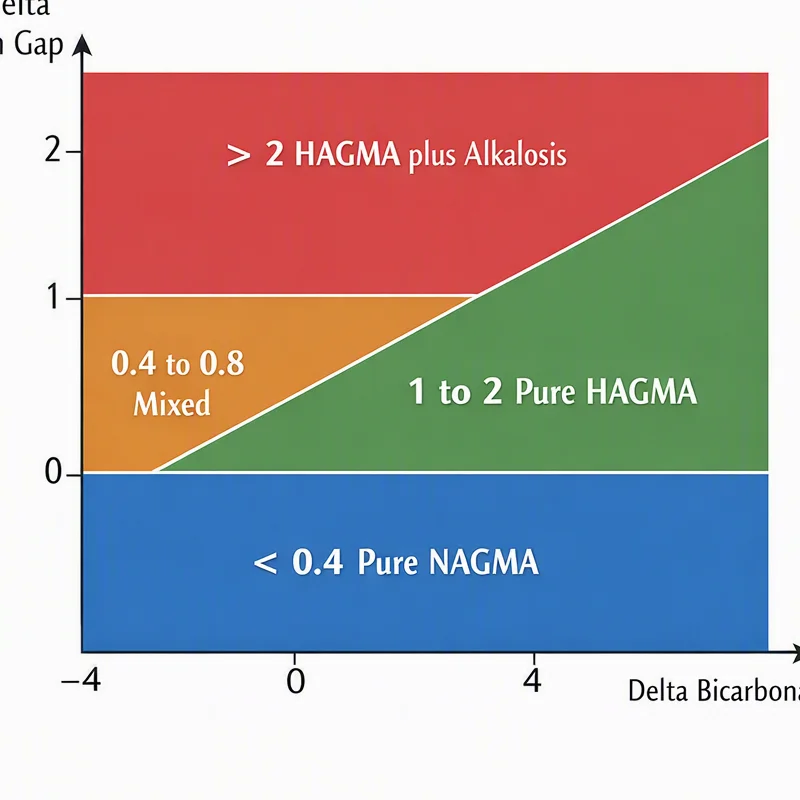
As a rule, a result is considered:
- Normal anion gap: inside the lab’s stated reference range. High anion gap: above the normal range and commonly tied to added unmeasured acids. Low anion gap: below the normal range and less frequent, sometimes due to protein changes or measurement issues.
A high anion gap is often the more significant finding because it may point to a problem with acid handling, acid production, or acid clearance. A low value is usually interpreted more carefully because it is less often a sign of a primary disease process.
It is important to compare the result with the lab-specific reference interval and the full clinical picture. The same number may be interpreted in a different way depending on the patient’s sodium, chloride, bicarbonate, albumin, and overall condition. This is where the clinical interpretation of the blood test matters more than the number alone.
Frequent Sources of a High Anion Gap
A elevated anion gap often indicates a rise of acids that are not directly measured in the standard test panel. This finding is frequently seen in metabolic acidosis, especially when the body is generating too much acid or cannot remove it effectively.
Several of the most common causes consist of:
- Lactic acidosis: occurs when lactate piles up, often in cases of poor oxygen supply, shock, severe illness, or intense physiologic stress. Ketoacidosis: happens when ketones build up, commonly in diabetes, prolonged fasting, or alcohol-related metabolic states. Kidney failure: decreases the body’s ability to remove acid and can result in retention of unmeasured anions.
These conditions can raise the gap because they boost the amount of acids not included among the standard measured ions. The result may point clinicians toward the correct diagnosis, but it does not identify the cause on its own. Additional testing and clinical context are needed to determine whether the issue is lactic acidosis, ketoacidosis, kidney failure, or another process.
In practice, the anion gap is one part of the broader assessment of metabolic panel results. It helps sort the type of acidosis and determine whether the patient has a metabolic acidosis with an elevated gap or another acid-base pattern entirely.
FAQ
This section covers frequent questions about the anion gap calculator, the relevant lab values, and how different panels affect the result. This information can help you operate an electrolyte panel more effectively and see what the numbers mean.
Do You Need Potassium for the Calculation?
Usually, no. The standard formula for the anion gap uses sodium, chloride, and bicarbonate only. Potassium is included in some versions of the calculation, creating a modified anion gap, but that is not the most common formula in routine clinical use. Most anion gap calculator tools rely on the standard formula unless they specifically say otherwise.
Can You Calculate an Anion Gap from a Basic Metabolic Panel?
Yes, it can. A basic metabolic panel usually includes the values needed for the calculation: sodium, chloride, and bicarbonate. A comprehensive metabolic panel also includes those same values, so either lab test can provide the data needed for anion gap calculation. If the report includes the key electrolytes, the calculator can use them right away.
What Causes a Low Anion Gap?
A low anion gap can happen for several reasons, including lab error, changes in chloride, or conditions such as multiple myeloma. Because low results are less common than high ones, they often prompt a careful review of the laboratory data and the patient’s overall condition. Low albumin can also contribute, so the result should be interpreted in light of other findings rather than in isolation.
What lab values do I need to calculate the anion gap?
You need three main lab values: serum sodium, serum chloride, and serum bicarbonate. An anion gap calculator uses those values to perform the standard calculation. In some cases, albumin may also be useful for interpretation, especially if the clinician is considering an albumin-corrected anion gap.
Can the calculator use potassium?
Most of the time, no. The common basic formula does not include potassium. Some calculators offer a alternate anion gap that includes it, but that is not the typical approach. If potassium needs to be considered, it is usually because the clinician wants a more detailed interpretation rather than a routine screening value.
Is it possible to calculate the anion gap from a basic metabolic panel?
Yes. A basic chemistry panel often provides the necessary lab values, so it can be used to work out the anion gap. A complete metabolic panel works too because it includes the same electrolyte measurements. As long as the laboratory test reports sodium, chloride, and bicarbonate, the calculation can be done.
Why is albumin important when interpreting the anion gap?
Albumin is important because it serves as a key unmeasured anion. As albumin is decreased, especially in hypoalbuminemia, the reported anion gap can appear incorrectly normal or low. Under those circumstances, an albumin-corrected anion gap may more reliably reflect the true acid-base status and help identify a hidden high anion gap.
How does a high or low anion gap mean?
A high anion gap commonly suggests metabolic acidosis resulting from conditions such as lactic acidosis, ketoacidosis, or kidney failure. A decreased anion gap is relatively uncommon and may be caused by lab error, protein abnormalities, or changes in chloride. The result should always be interpreted using the full clinical picture and the laboratory’s normal range.