What the Anion Gap Reflects
The anion gap represents a calculated value used to help evaluate electrolytes and interpret acid-base balance. It isn’t a directly measured lab analyte by itself; instead, it comes from from common values on a serum chemistry panel. Clinicians use it as a diagnostic tool when interpreting lab results for signs of an electrolyte imbalance or an acid-base disorder.
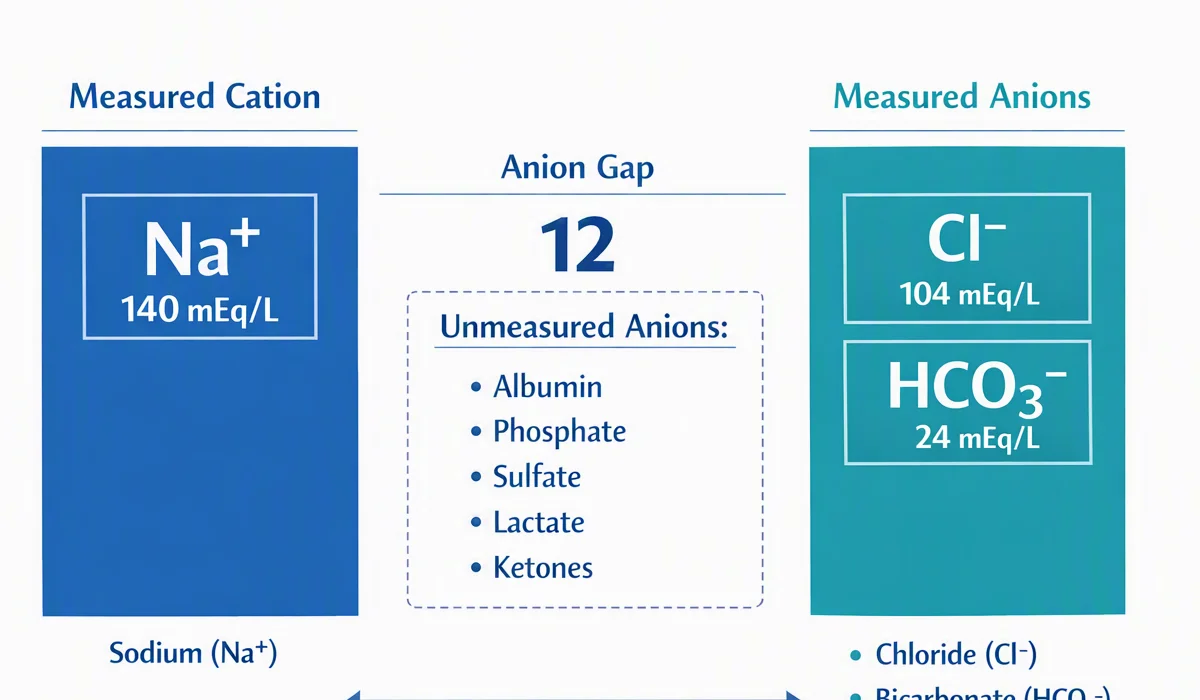
At its core, the anion gap illustrates the connection between major positively charged ions and negatively charged ions in the blood. The usual focus is on serum sodium, serum chloride, and serum bicarbonate, with potassium sometimes factored in depending on the formula being used. Because many unmeasured ions also play a role to the total anion concentration, the anion gap offers an interpretive framework for finding hidden causes of metabolic acidosis.
In clinical terms, the anion gap helps show whether acid is accumulating in the body, whether bicarbonate is being lost, or whether another process is affecting the balance of charged particles in the bloodstream. That makes it especially helpful in metabolic evaluation and clinical assessment.
Anion Gap Equation With and Without Potassium
There are two standard approaches to determine the anion gap: a standard formula that excludes potassium and a potassium-based formula that puts it back. An anion gap calculator may work with either formula, so it is important to know which one is being calculated.
The traditional formula is:
Anion gap result = sodium - (Cl + bicarbonate)
The potassium-inclusive formula is:
Anion gap = sodium + K - (Cl + bicarbonate)
This difference may seem slight, but it can affect the final calculated anion gap. Since potassium is usually present in a lesser concentration than sodium, the numeric change is small, yet it can matter when comparing results across different lab systems or when tracking a borderline result.
Some clinicians favor the version without potassium because it is more commonly used in modern practice. Others include potassium because it https://anion-gap-checker116.quillnesty.com/posts/how-to-read-the-anion-gap-in-emergency-medicine shows a more complete charge balance and can be useful in select situations. Either way, the most important step is to know which equation your calculator uses and to assess the result accurately.
How to Determine the Anion Gap Stepwise
To work out the anion gap, start with the relevant laboratory values from the serum chemistry panel. You will need serum sodium, serum chloride, and serum bicarbonate; potassium is optional depending on the calculation method. Applying the proper calculation matters because a calculator cannot compensate for mismatched inputs and formula assumptions.
Below is a simple step-by-step process:
- Identify the sodium value on the chemistry panel. Identify the chloride value. Find the bicarbonate value, often listed as CO2 or total CO2. Select the traditional formula or the potassium-inclusive formula. Type in the numbers into the calculator or calculate manually. Check the result with the lab reference range used by that laboratory.
An example using the traditional formula:
If sodium is 140, chloride is 102, and bicarbonate is 24, then:
140 - (102 + 24) = 14
Here is an example with potassium-inclusive formula:
If sodium is 140, potassium is 4, chloride is 102, and bicarbonate is 24, then:
140 + 4 - (102 + 24) = 18
This difference shows why the calculator should clearly identify whether it is reporting an uncorrected anion gap or a potassium-inclusive result. In either case, the value is only one part of the overall metabolic picture.
Normal Anion Gap Range and How Outside-the-range Results Mean
The normal range for the anion gap depends on the local reference range and the calculation approach. Different laboratories may report different reference interval values because of their measurement techniques and whether they include potassium.

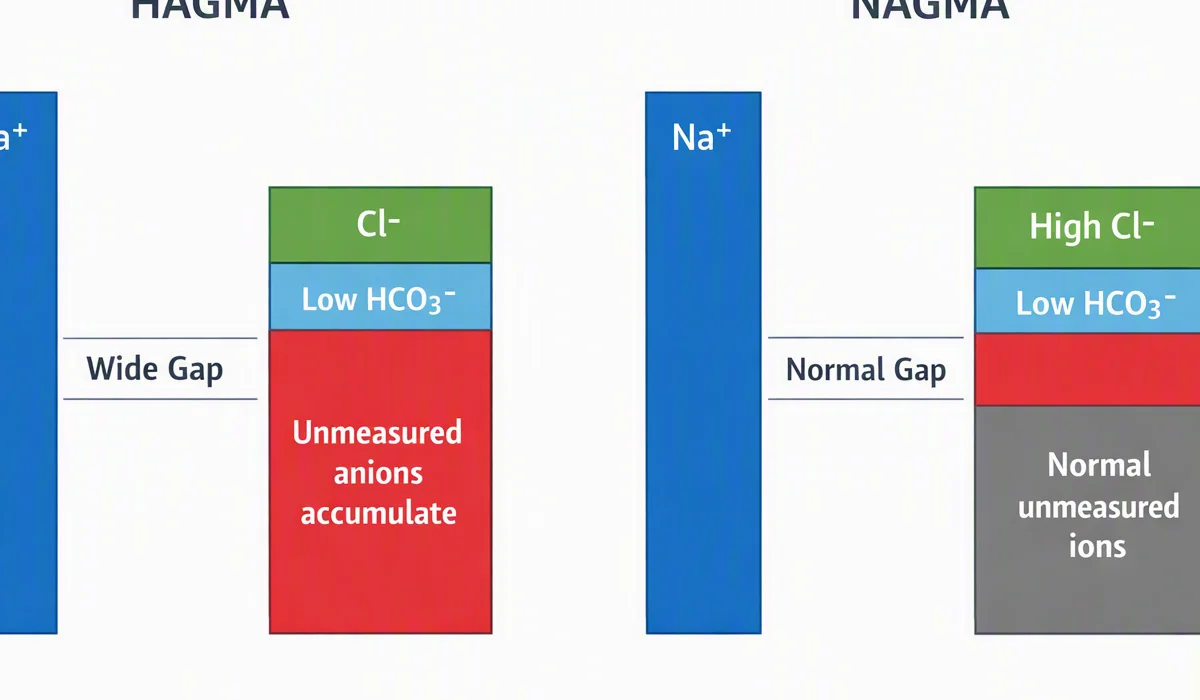
A high anion gap usually suggests that unmeasured acids are present in excess. This pattern is often seen in metabolic acidosis caused by build-up of acid. A within-range anion gap, on the other hand, can still occur in acidosis if bicarbonate loss is matched by chloride gain, producing a different biochemical pattern.
Interpretation should never rely on a single number alone. A mildly elevated value may be insignificant in one context but important in another, especially if the patient has symptoms or other abnormal lab findings. The exact meaning depends on the patient’s clinical interpretation and the surrounding data.
It is also important to compare the calculated result with the local lab reference range rather than a generic number from another source. The same anion gap value may be normal in one system and abnormal in another.
Why Potassium May Be Included in the Formula
Including potassium in the calculation is based on the idea of charge balance. In body fluids, opposing charges must remain balanced. Because potassium is a tracked cation, counting it to the formula gives a more full picture of the major ions contributing to the total charge balance.
From a practical standpoint, potassium inclusion may improve certain aspects of clinical interpretation, especially when a clinician wants to compare the result with older literature or with settings that still use the potassium-inclusive version. It can also be valuable when reviewing borderline values or when following a patient over time using the same approach.
That said, many modern references favor the traditional formula because potassium contributes more modestly to the total than sodium and because excluding it makes easier routine use. The best choice depends on the purpose of the calculation, the calculator settings, and the local reporting convention.
When using any anion gap calculator, consistency matters more than preference. If you change formulas without noticing, you may overlook a trend or inflate the significance of a result.
Origins of Elevated Anion Gap Metabolic Acidosis
A increased anion gap value is most commonly associated with acid buildup in the body caused by the accumulation of acids that are not typically measured on routine labs. This is a key sign in many forms of acid-base imbalance and often prompts a deeper search for the source of the acid load.
Two classic causes are excess lactate and ketone-related acidosis. In lactic acidosis, the body creates excess lactate due to poor oxygen delivery, disrupted metabolism, or other stress states. In ketoacidosis, ketone bodies collect, often in the setting of insulin deficiency, prolonged fasting, or severe illness.
Other causes can include toxins, kidney failure, or severe tissue breakdown, but the key concept is the same: extra acid enters the system, bicarbonate is consumed, and the anion gap rises. This is why the anion gap is such a useful diagnostic tool in metabolic evaluation.
When reviewing a high value, clinicians often combine the anion gap with a blood gas test and serum bicarbonate level to assess severity and to determine whether the acidosis is compensated or worsening.
Reasons of Normal Anion Gap Metabolic Acidosis
A normal calculated gap does not exclude acidosis. In fact, a typical pattern is hyperchloremic acidosis, where bicarbonate decreases but chloride goes up to keep charge balance. This produces a normal calculated gap even though the patient still has an acid–base disorder.
One major cause is loose stools, which leads to loss of bicarbonate from the gastrointestinal tract. Another significant cause is RTA, a group of disorders in which the kidneys fail to handle acid and bicarbonate properly. In both cases, the body loses bicarbonate and chloride rises relative to the change, keeping the gap in the usual range.
Because of this, a normal number should not end the evaluation if the patient appears clinically acidotic. The broader pattern of lab findings, symptoms, and blood gas data may still point to a serious acid-base problem.
Calculating the Anion Gap for Albumin
Albumin is one of the major unmeasured anions in the blood, so shifts in albumin can alter the apparent anion gap. When a patient has hypoalbuminemia, the measured gap may appear lower than it truly is. This is why albumin correction is often advised in clinical settings.
A corrected anion gap can expose occult acid accumulation that would otherwise be missed. If albumin is low, the measured gap may fail to reflect the severity of an underlying metabolic problem. In that setting, applying an albumin correction improves the accuracy of the result and strengthens the interpretive value of the calculator.
Exact correction is based on the technique selected by the lab or reference source, but the rule is consistent: reduced albumin means less undetected anions, so the measured gap can seem deceptively within range. Accounting for albumin offers a more dependable picture for clinical assessment.
For this reason, an anion gap calculator is especially helpful when it lets the user to review albumin alongside sodium, chloride, bicarbonate, and potassium. This combination provides a more thorough interpretive framework.
How to Interpret Results in Clinical Context
This anion gap should routinely be reviewed alongside all of the medical picture. A reading from a calculator is not a determination by itself. Rather it is one indicator in a wider clinical correlation process that may involve complaints, drug history, physical exam findings, blood gas results, and repeat laboratory testing.
For instance, a patient with decreased serum bicarbonate, high anion gap, and clinical signs of illness may have a serious metabolic issue. One more patient with the same number but unremarkable blood gas findings and no clinical symptoms may need only monitoring or further review of laboratory methods.
Clinical circumstances also counts when the result is near the lab reference range. Slight variations in chloride or bicarbonate can shift the calculated value higher or lower, especially if the analyzer or collection method adds variability. For this reason a good anion gap calculator supports interpretation, but does not replace clinical judgment.
Common Mistakes When Using an Anion Gap Calculator
Several interpretation pitfalls can cause confusion when using an anion gap calculator. One typical mistake is measurement error, which may come from sample processing, instrument variation, or wrong input of the lab values. Just a small error in sodium, chloride, or bicarbonate can alter the final number.
Another mistake is ignoring the laboratory reference range. A value that looks abnormal in one setting may be normal in another because each laboratory sets its own reference interval. If you are reviewing results across systems, always verify whether the calculator uses the same method and whether it is reporting a potassium-inclusive or traditional result.
Another issue is assuming that every elevated result means the same thing. The anion gap is a useful diagnostic tool, but it must be paired with other data to determine whether there is true metabolic acidosis, a mixed disorder, or a lab artifact. A careful review of the chemistry panel, blood gas, and history helps prevent overinterpretation.
Lastly, users sometimes overlook albumin status. Without albumin adjustment, a patient with low albumin may have a deceptively normal or low anion gap. Being aware of that possibility improves the quality of clinical interpretation.
Frequently Asked Questions
What is an anion gap calculator with potassium?
An anion gap calculator with potassium is a tool that calculates the anion gap using sodium, chloride, bicarbonate, and optionally potassium. It helps assess electrolyte values and supports evaluation of acid-base balance and possible acidotic states.
How do you calculate the anion gap with potassium included?
Use the formula including potassium: sodium plus potassium minus chloride and bicarbonate. In equation form, it is anion gap = sodium + potassium - (chloride + bicarbonate). Make sure the numbers come from the same chemistry panel.
When should potassium be included in the anion gap formula?
Potassium may be added when the calculator or reference source uses the potassium-inclusive approach, or when a clinician wants to compare results using that method. The choice should be the same each time because formula differences can affect the anion gap value and its clinical interpretation.
What does it indicate when a high anion gap?
A high anion gap often suggests excess unmeasured acids and is commonly seen in metabolic acidosis. Important causes include lactic acidosis and ketoacidosis. The result should be considered with the blood gas, serum bicarbonate, and overall clinical picture.
Should the anion gap be corrected for albumin?
Yes, in many cases it should. Hypoalbuminemia can make the gap appear lower than it really is, so albumin correction may reveal a more accurate corrected anion gap. This is especially useful when the result seems unexpectedly normal despite signs of acidosis.