What Is the Anion Gap and Why Does It Matter in Shock?
The anion gap is a useful way to look for hidden acids in the blood and to separate causes of metabolic acidosis during shock. In clinical practice, it is part of a broader acid-base interpretation that starts with the electrolytes in a standard serum chemistry panel. When tissue oxygen delivery drops, the body may shift toward anaerobic pathways and produce acid, making the anion gap a important diagnostic clue in undifferentiated shock.
In shock, the anion gap can be significant because it can point toward a perfusion problem, a toxic exposure, or another secondary cause of metabolic derangement. A rising gap often suggests unmeasured anions are accumulating, while a normal gap may indicate bicarbonate loss or a different acid-base disorder. Either way, the number should be interpreted in the context of hemodynamic instability, resuscitation status, and the rest of the clinical assessment.
A useful way to think about the anion gap is as a clinical marker that narrows the differential. It does not diagnose shock by itself, but it can help identify whether the acid-base disorder is more consistent with lactic acidosis, ketoacidosis, renal failure, toxic alcohols, or another process. In critical care, that distinction can alter the next step quickly.
How to Apply an Anion Gap Calculator Accurately
An anion gap calculator is only as accurate as the results entered into it. The computation usually depends on serum sodium, serum chloride, and serum bicarbonate, which are obtained from the electrolyte panel. Because the output can affect urgent decisions, the numbers should be checked for agreement with the broader serum chemistry and the clinical picture.
Most calculators use a standard formula that balances measured cations and anions. If the result seems unusual, first verify the lab values and confirm whether the bicarbonate is from the chemistry panel rather than a blood gas. Even small changes in chloride or bicarbonate can shift interpretation, especially in a patient with evolving shock and ongoing resuscitation.
To use the calculator correctly, consider these steps:
- Confirm the electrolyte panel is up to date and not outdated. Use the same set of values from one blood draw when possible. Check whether albumin is decreased, since that can mask a real gap. Compare the result with the arterial blood gas and lactate. Interpret the number as part of acid-base analysis, not in isolation.
The anion gap calculator is especially helpful when the clinical question is whether the patient’s acidosis reflects unmeasured acids or another pattern. In shock, this can strengthen rapid bedside reasoning, but it should never replace clinical assessment or trend monitoring.
What Does a High Anion Gap Suggest in Shock?
A high anion gap in hemodynamic shock usually suggests accumulation of acids or toxins. The most common cause in unstable patients is lactic acidosis, which often indicates tissue hypoperfusion. When blood flow and oxygen delivery are inadequate, cells shift to anaerobic metabolism, generating lactate and raising the gap upward.
This pattern is common in sepsis, hemorrhage, cardiogenic shock, and other states with impaired perfusion. The anion gap serves as a useful diagnostic clue because it may rise before the clinical picture fully declares itself. In a patient with metabolic acidosis and hemodynamic instability, a high gap should raise concern for ongoing oxygen debt and inadequate resuscitation.
That said, a high anion gap does not automatically mean the cause is lactate. It only indicates that unmeasured acids are present. The next step is to match the lab pattern with the story: infection, hypoperfusion, renal dysfunction, diabetic decompensation, or ingestion. In critical care, the value is strongest when combined with the arterial blood gas, lactate, and bedside findings.
In shock, a rising anion gap often signals worsening perfusion deficit, but the cause still needs targeted identification.
How to Differentiate Causes of High Anion Gap Acidosis?
When a high gap is detected, the key objective is to find the underlying secondary cause. In shock, the leading contenders include ketoacidosis, renal insufficiency, toxic alcohol exposure, and salicylates. Each requires a different management approach, so the pattern on the labs and the history matter.
Ketoacidosis may occur in diabetes, starvation, or alcohol-related states and often presents with an elevated gap plus low serum bicarbonate. Renal insufficiency can also produce a high gap because acid clearance is impaired. With toxic alcohol exposure, the gap may be high early, sometimes before an osmolar gap closes in, and the patient may have neurologic findings or unexplained acidosis. Salicylates can cause a mixed acid-base disorder, often combining respiratory alkalosis with metabolic acidosis.
Useful clues for differentiation include:
- A history of diabetes, fasting, or alcohol use for ketoacidosis Known renal disease, oliguria, or increasing creatinine for renal failure Exposure history, altered mental status, or visual symptoms for toxic alcohols Ringing in the ears, hyperventilation, or mixed respiratory findings for salicylates
In shock, these causes may coexist with lactic acidosis. As an example, a septic patient with renal dysfunction can have more than one acid-base disorder at once. This is why the high anion gap should always trigger broader diagnostic reasoning rather than a single-track conclusion.
What Is a Normal Anion Gap Suggest in Shock?
A expected anion gap does not exclude serious acidosis in shock. It may suggest non-anion gap metabolic acidosis, which often stems from bicarbonate loss rather than build-up of unmeasured acids. In the unstable patient, this can occur with diarrhea, kidney tubular dysfunction, or chloride-rich fluid administration causing chloride excess.
A normal anion gap acidosis is important because it can coexist with shock-related hypoperfusion. For example, a patient may have received significant chloride-containing fluids during resuscitation and develop a non-gap metabolic acidosis even as the initial perfusion deficit resolves. In other cases, diarrhea or renal tubular dysfunction may be the primary acid-base disorder while shock is the overall clinical context.
Do not assume a normal gap means the situation is benign. It may simply mean the current problem is not build-up of unmeasured acids. The bicarbonate can still be low, the pH can still be acidemic, and the patient can still have significant organ stress. Always assess the arterial blood gas, clinical trend, and response to resuscitation.
How Can Albumin Levels Influence Anion Gap Interpretation?
Hypoalbuminemia may render the anion gap look incorrectly normal or just slightly high. Albumin is a important unmeasured anion, so when it is low, the measured gap decreases even if clinically important acids are present. This is especially significant in critical illness, where low albumin is common and can distort acid-base balance interpretation.
Albumin correction may help adjust the gap upward when albumin is low. That adjustment is crucial because an uncorrected result can miss a true high-gap process. In a patient with shock, this can slow the detection of lactic acidosis or another acid-base disorder that needs urgent attention.
Use albumin correction when the result does not fit the patient’s condition. If the patient appears severely ill but the gap is “normal,” low albumin may be hiding the abnormality. Correcting for https://anion-gap-tool502.bearsfanteamshop.com/does-pregnancy-affect-the-anion-gap albumin gives a better picture of acid-base balance and helps distinguish a genuine normal-gap state from a masked high-gap state.
In practice, albumin should be checked alongside the anion gap calculator result, the serum bicarbonate, and the arterial blood gas. That combined view is more reliable than any single number.
What Additional Labs Help Evaluate Shock and Acid-Base Status?
The anion gap is only one piece of the acid-base picture. During shock, several other labs help clarify the problem and direct resuscitation. The key are lactate, arterial blood gas, base deficit, and serum ketones.
Lactate is especially helpful because it reflects the severity of hypoperfusion and the degree of oxygen debt. An elevated lactate is consistent with lactic acidosis, though the exact source still requires clinical interpretation. The arterial blood gas reveals pH, PaCO2, and bicarbonate, helping identify whether the patient has a simple metabolic acidosis or a mixed disorder with respiratory compensation. Base deficit provides another way to quantify metabolic acidosis and can help monitor response over time. Serum ketones are valuable when ketoacidosis is possible.
Other supportive data may include creatinine, glucose, osmolar gap if toxic alcohols are a concern, and repeat electrolytes to observe the progressing serum chemistry. In critical care, a single snapshot is rarely enough. The broader lab pattern is the best way to connect the anion gap to the actual cause of shock.
When Should You Recheck the Anion Gap in Shock Cases?
Reassess the anion gap when the patient is receiving active stabilization, when the cause of shock is still being worked out, or when treatment is underway and you need serial assessment. Repeated checks is especially useful if the initial gap is high, if lactate is elevated, or if the clinical response is not clear.
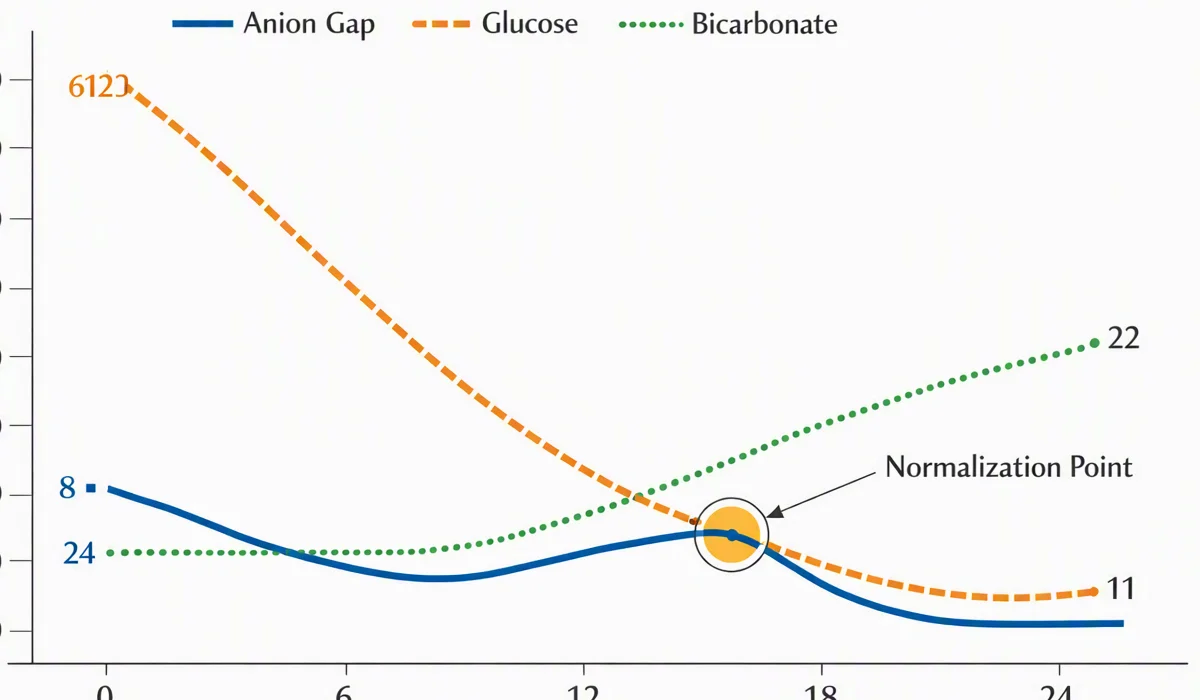
A falling gap can be a positive sign that the metabolic derangement is improving. In lactic acidosis, for example, the gap may fall as perfusion gets better and oxygen delivery is reestablished. In ketoacidosis, it often closes as insulin and fluids resolve the metabolic process. In toxic ingestion, the pattern may evolve differently, but trend monitoring still assists show whether treatment is working.
Review again sooner if the patient worsens, if new laboratory data do not align with the bedside picture, or if a mixed disorder is suspected. In shock, the anion gap is most useful when it is paired with ongoing clinical assessment and a clear understanding of the compensatory response.
Common Pitfalls When Interpreting Anion Gap in Shock
A frequent mistake is testing error. A broken-down sample, sample mix-up, or stale value can cause faulty interpretation. One more issue is not identifying mixed acid–base disorders, which are common in shock and can hide the true process.
Failing to consider albumin adjustment is an all-too-common oversight. Low albumin can make a serious elevated anion-gap acidosis appear less obvious than it really is. The opposite can also happen: a patient can have both lactic acidemia and chloride-related acidosis, which may partially offset each other and create a misleadingly mild gap.
The delta-gap can be useful if a mixed disorder is suspected. It compares the change in anion gap with the difference in bicarbonate and can show whether there is an concurrent metabolic alkalosis or a distinct non-gap acidosis. This is helpful in undifferentiated shock, where multiple processes may be present at the same time.
Additional issues include missing the clinical context, failing to remember that shock itself may contribute to lactic acidosis, and depending on one isolated value in place of the full pattern. Good acid-base interpretation calls for the electrolyte panel, arterial blood gas, lactate, and bedside hemodynamics to be reviewed together.
FAQ: Anion Gap in Shock
What does a high anion gap mean in shock?
An elevated anion gap in shock usually means unmeasured acids are accumulating, usually from lactic acidosis due to tissue hypoperfusion. It can also reflect ketoacidosis, renal failure, toxic alcohols, or salicylates, so the result should be interpreted with the clinical picture and other labs.
Can shock cause a normal anion gap metabolic acidosis?
Absolutely. Shock can occur with normal anion gap metabolic acidosis, especially if chloride-rich fluids are given during resuscitation or if there is another cause such as diarrhea or renal tubular acidosis. A normal gap does not rule out a significant acid-base disorder.
How does lactate affect the anion gap?
Lactate is an unmeasured anion, so when it rises it can increase the anion gap. Elevated lactate often reflects inadequate oxygen delivery, tissue hypoperfusion, or sepsis-related metabolic stress.
Why should albumin be considered when interpreting the anion gap?
Albumin is a major unmeasured anion. If albumin is low, the anion gap may appear artificially normal or only slightly elevated. Albumin correction helps uncover hidden metabolic acidosis, especially in critical illness.
What labs should be checked with an anion gap calculator in shock?
Along with the Anion Gap Calculator result, check lactate, arterial blood gas, base deficit, serum ketones, and repeat electrolytes including serum bicarbonate. These tests help define the acid-base disorder and distinguish lactic acidosis, ketoacidosis, renal failure, toxic alcohols, and other causes.