What Are these unmeasured cations
These unmeasured cations remain positively charged components in the blood that are present but not regularly measured on a standard serum chemistry panel. They are important because the body maintains electrical neutrality: the total positive charge from cations must balance the total negative charge from anions. When clinicians review serum electrolytes, they usually see the major measured ions, but some ions are left out of the usual calculation.
The most familiar measured ions include sodium, chloride, and bicarbonate. These are the key values used to estimate the anion gap. The gap is a practical derived number in acid-base assessment because it provides a quick look at ion balance and can suggest whether hidden acids or other factors are at play.
In everyday practice, measured ions do most of the work in lab interpretation. Still, the smaller set of unmeasured cations can influence the result, especially when there is a major shift in serum concentration or when a patient has an unusual exposure or illness. That is why understanding these ions is useful for both laboratory interpretation and broader acid-base balance review.
A basic metabolic panel gives the main electrolyte values, but it does not fully represent all charged species in plasma. The gap reflects what is not directly measured, including some anions and cations. Most of the time, the body’s buffer systems and ion distribution keep the effect small. However, in the right clinical setting, these missing cations become an important diagnostic clue.
Which Frequent Cations Are Usually Not Measured?
The most discussed common cations that are not measured routinely are magnesium, calcium, potassium, and lithium. Every one has a different role in the body, and every one affects blood chemistry in another way.
Potassium is frequently measured in standard testing, but it is not part of the classic anion gap formula. As its serum level is usually much lower than sodium, its omission seldom changes the calculation significantly. Even so, extremely high or very low potassium can be important in broader electrolyte disturbances and may influence the overall clinical picture.
Ca is another cation that is typically checked on its own rather than counted in the anion gap equation. Changes in calcium can impact neuromuscular function and suggest systemic illness, but its direct effect on the gap is typically small unless the abnormality is pronounced.
Magnesium levels is a frequent concern in hospitalized patients, especially those with poor intake, gastrointestinal losses, or renal issues. Hypermagnesemia can act as an added positive charge load, but significant changes in the anion gap are rare unless the elevation is substantial.
Lithium remains the most important undetected positive ion from a laboratory interpretation standpoint because it may greatly change the anion gap when found in toxic amounts. Unlike other ions, lithium is a drug and toxic substance rather than a standard electrolyte. Its positive electrical charge can immediately shift ion balance and cause a low or even negative anion gap.
These cations are generally limited factors under normal conditions, but they turn relevant when the reference range is breached or when there is an unexpected acid-base pattern. That is why the question is not only which cations are missing, but which ones are meaningful in practice.
In What Way Unmeasured Cations Alter the Anion Gap
The anion gap is a calculated approximation of the difference between commonly measured positively charged and negatively charged ions. As unmeasured cations elevate, the equilibrium can shift in a way that makes the gap appear lower. That is because extra positive charge reduces the space left for unmeasured anions in the equation.
The connection becomes especially important in acid-base balance. As an example, in metabolic acidosis, a high anion gap often suggests the accumulation of acids. However if the patient also has a significant cation load or low albumin, the result can be misleading unless the full picture is reviewed.
Albumin deserves close attention because it is a major negatively charged plasma protein. Low albumin reduces the expected anion gap, which can mask an underlying acid-base problem. Put differently, a normal gap is not always reassuring if albumin is low. This is where a corrected anion gap becomes useful in laboratory interpretation.
Unmeasured cations matter because they can obscure what is happening with hidden acids, buffer systems, and plasma proteins. They do not usually create major issues in healthy individuals, but they can alter the numerical result enough to change clinical thinking. For that reason the gap should be interpreted as part of a full acid-base assessment, not as a standalone answer.
In practical use, if the gap is unexpectedly low, clinicians may think about extra cation load, low albumin, or both. If the gap is high, the focus shifts toward acid accumulation, though unusual cation shifts can still complicate interpretation. The core idea is simple: ion balance is dynamic, and the anion gap is only one window into that balance.
When to Recognize an Increased Unmeasured Cation Load
An higher unmeasured cation load is most important to consider when the lab pattern does not fit the patient’s status. The concern increases if there is poisoning, renal disease, or a clear ion imbalance that is not fully explained by the usual measured ions.
Renal disease is a frequent setting because impaired renal function can disrupt excretion of multiple electrolytes and contribute to renal failure-related shifts in serum concentration. In this context, both cation and anion handling may change. The result can be a unclear pattern that needs careful review rather than a quick conclusion.
Toxicity is another important clue. Lithium exposure exposure can produce a low anion gap and should be considered when there is a compatible medication history or altered mental status. This is an example of how a specific cation can serve as a powerful diagnostic clue, especially if the lab pattern appears discordant with the clinical picture.
A significant acid-base disturbance can also point to a hidden ion problem. If a patient has symptoms of systemic illness, unexpected lab changes, or worsening acid-base disturbance, the possibility of unmeasured cation contribution should be kept in mind. These situations often require careful review of the full metabolic panel and repeat testing if needed.
Other signs that deserve attention include sudden confusion, weakness, arrhythmia concerns, or a sudden change in a previously stable electrolyte profile. In those cases, the issue is not just the number on the page. It is the possibility that the reported result reflects a broader disturbance in ion balance or a developing toxic or renal process.
Frequent Causes of Low or Normal Anion Gap
A low-range or normal anion gap does not always mean the patient is fine. Among the most frequent causes is hypoalbuminemia. Since albumin is a primary negatively charged protein, low levels lower the calculated gap and can hide another process. This is why albumin should always be considered when assessing the result.
Lab error is also a frequent cause. A specimen problem, analytic issue, or data entry problem can alter the measured ions and create an apparently abnormal gap. If the number does not fit the patient’s condition, redoing the test is often the initial step in responsible laboratory interpretation.
Paraproteinemia is an significant but less common cause. Abnormal plasma proteins, especially in monoclonal gammopathies, can alter charge distribution and affect the apparent balance between measured ions. Because these proteins are part of the broader pool of plasma proteins, they can influence the gap in a way that points to an underlying blood-related disorder.
A normal anion gap can also be seen when there is no major acid-base problem, when the cation and anion shifts balance one another, or when the abnormality is mild enough to fall within the reference range. That is why the result must be interpreted with the clinical picture, medication history, kidney function, and albumin level in mind.
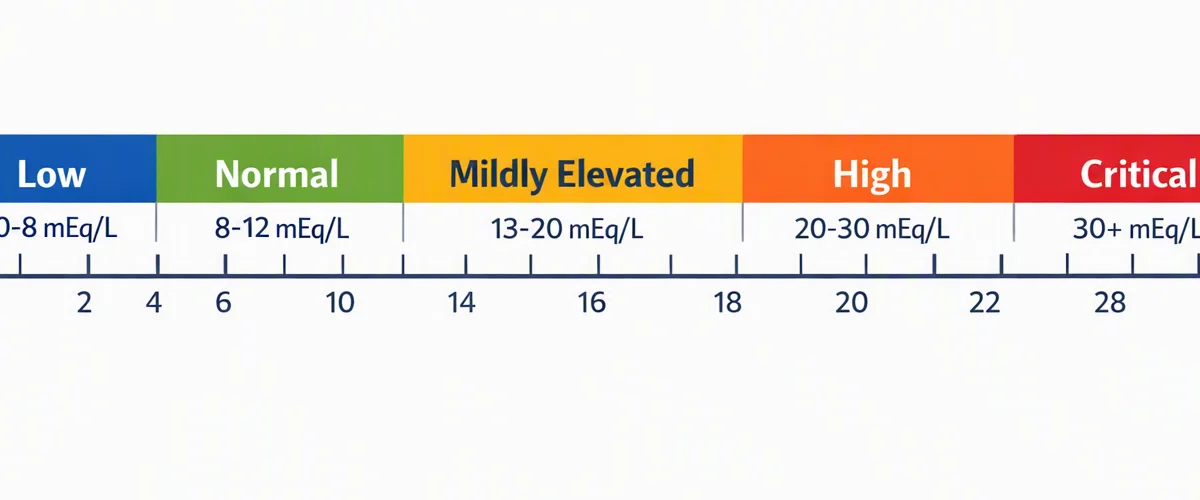
In short, a reduced or normal gap is often explained by one of three broad ideas: low albumin, lab error, or abnormal proteins. A patient-centered interpretation helps separate benign variation from clinically meaningful disease.
How to Read Results with an Anion Gap Calculator
An anion gap calculator is a useful tool for fast checking of electrolyte data. It usually uses sodium, chloride, and bicarbonate to derive the gap. Because these values come from the standard chemistry panel, the calculator provides a clear snapshot of the current ion balance.
To use it well, first of all confirm that the input values are correct and belong to the same sample. Small transcription errors can make the result unreliable. Next, compare the output to the expected reference range used by the laboratory or institution. Different methods and analyzers may produce slightly different results, so the exact cutoff matters.
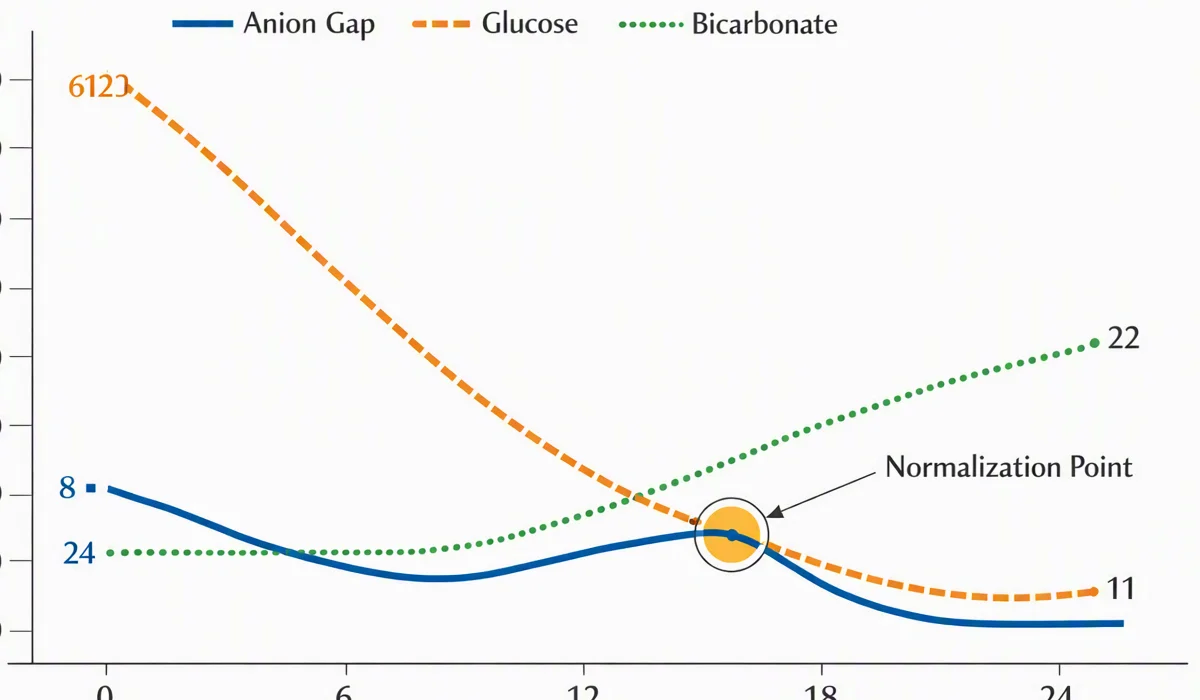
If the result is low, think through common explanations: hypoalbuminemia, lab error, excess cation load, or paraproteinemia. If the result is high, consider whether the patient has metabolic acidosis or another process that increases unmeasured anions. The number alone is not the diagnosis; it is a first step for acid-base assessment.
It also helps to review the trend of chloride and bicarbonate. A low bicarbonate often points toward metabolic acidosis, while chloride changes may indicate compensation or a non-gap pattern. Pairing the result with albumin allows a more accurate corrected anion gap, especially in patients with systemic illness.
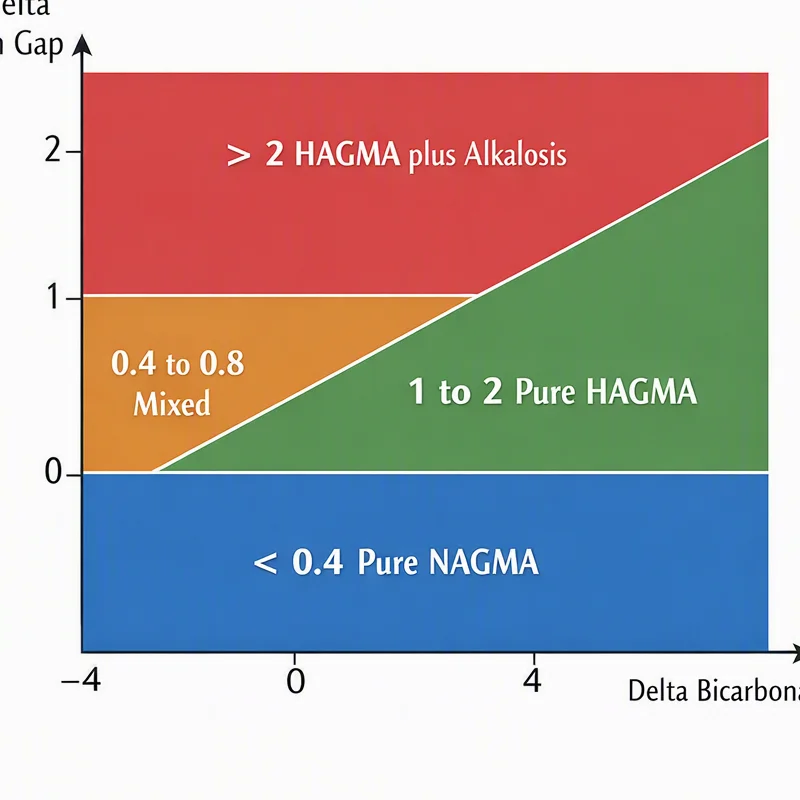
Use the calculator as part of a broader clinical reasoning process. Ask whether the result fits the symptoms, medication list, kidney function, and other measured ions. That approach makes the calculator more than a number generator; it becomes a tool for better laboratory interpretation.
A useful anion gap result is not just about calculation. It is about matching the number with the patient’s condition, the serum electrolytes, and the likely acid-base disorder.
In practical terms, if the gap is unexpected, review the underlying values first, then assess whether albumin correction is needed, then consider uncommon cations or toxic exposures. This sequence helps avoid missing a hidden diagnosis.
Common Questions
Which are the main unmeasured cations?
The most commonly discussed unmeasured cations are magnesium, calcium, potassium, and lithium. Potassium and calcium are often measured separately, but they are not part of the classic anion gap formula. Lithium is the most significant https://anion-gap-reference112.timeforchangecounselling.com/anion-gap-calculator-for-electrolyte-review unusual cation because it can significantly affect the anion gap when present in toxic amounts.
Why do unmeasured cations matter during an anion gap calculation?
They matter because the anion gap is based on measured ions only, mainly sodium, chloride, and bicarbonate. Extra positive charge from unmeasured cations can lower the apparent gap and change laboratory interpretation. This can influence acid-base assessment, especially when there is hypoalbuminemia, kidney disease, or a possible toxic exposure.
Can lithium cause a low or negative anion gap?
Yes. Lithium is a classic cause of a low or even negative anion gap when serum levels are high enough. Because it is a positively charged ion that is not routinely included in the calculation, it can significantly shift ion balance. If the result is unexpected and lithium exposure is possible, toxicity should be considered promptly.
Do calcium or magnesium meaningfully change the anion gap?
Usually not by much. Calcium and magnesium can act as unmeasured cations, but they typically do not alter the anion gap dramatically unless the abnormality is severe. Their clinical importance is greater for electrolyte disturbances and overall acid-base balance than for routine gap calculation.
How should you respond if the anion gap result seems unexpected?
First, confirm the electrolyte values and consider repeating the test if lab error is possible. Then check albumin, review chloride and bicarbonate, and think about kidney disease, paraproteinemia, or toxicity. If the clinical picture suggests an acid-base disorder or a major electrolyte imbalance, further evaluation is warranted rather than relying on the number alone.