What this anion gap Reflects
The anion gap acts as a simple method to estimate unmeasured ions in the blood and to guide acid-base balance during a diagnostic workup. It is typically derived from serum electrolytes, particularly serum sodium, serum chloride, and serum bicarbonate. When these values shift in expected ways, the anion gap can uncover a subtle metabolic disturbance that would otherwise be missed on a basic chemistry panel.
In routine care, clinicians use the anion gap as a diagnostic marker for acid accumulation. A elevated value suggests that unmeasured acids are present in excess, often indicating metabolic acidosis. This makes the calculation very useful as an interpretation guide when reviewing an ill patient, a lab screening result, or a suspected electrolyte imbalance.
The basic anion gap formula typically deducts chloride and bicarbonate from sodium. Some versions also include potassium, but the most commonly used approach excludes it for simplicity and consistency. An anion gap calculator streamlines this step, helping clinicians quickly calculate anion gap values and consider the bigger question: what is causing the abnormality?
Because the calculation is based on measured ions, it is not a complete picture of physiology. Instead, it is a fast and practical approximation that supports laboratory assessment and more detailed acid-base interpretation. When the result is elevated, it often signals an elevated anion gap state that requires a closer look at renal function, perfusion, toxin exposure, and inherited metabolic disease.
Why Methylmalonic Acidemia Raises the Anion Gap
Methylmalonic acidemia is an organic-acid disorder and an inherited metabolic disorder in which the body cannot properly process certain metabolites, leading to the buildup of acids. That buildup produces metabolic acidosis and commonly produces a increased anion gap metabolic acidosis. In this setting, the anion gap becomes a hint to the underlying biochemical problem rather than just a number on a report.
The core issue is that methylmalonic acid along with related compounds build up in the bloodstream. These acids deplete buffering capacity, decrease bicarbonate, and add to an excess of unmeasured anions. As a result, the anion gap often climbs with the severity of the acid-base disorder. This is why a calculator can be useful in spotting the pattern early, especially when the patient is very sick and the presentation is vague.
In methylmalonic acidemia, the overall picture may reflect a metabolic emergency. Affected patients can present with vomiting, poor feeding, lethargy, dehydration, or encephalopathy, and the lab profile may show an elevated anion gap long before the full diagnosis is confirmed. The biochemical pattern usually indicates accumulation of toxic metabolites, decreased energy metabolism, and secondary systemic stress. For this reason an anion gap calculator can be a valuable initial step in interpretation, but not the final step in diagnosis.
The association between the calculated gap and the underlying process is strongest when the presentation includes acidosis plus additional supportive findings. Even so, the anion gap alone does not establish methylmalonic acidemia. It acts as a clinical correlation resource that assists clinicians identify a picture consistent with an organic acid increase and advance to targeted workup.
How to Operate an Anion Gap Calculator
To operate an anion gap calculator, provide the essential serum electrolytes: serum sodium, serum chloride, and serum bicarbonate. Some calculators also permit entry of potassium and albumin. The calculator runs the selected formula and produces the observed gap, which can then be compared with the expected range for the lab.
If potassium is included, the formula may produce a slightly higher value. In many clinical settings, however, potassium is omitted because it contributes less to everyday decision-making and can vary between institutions. The more important step is to recognize whether the result suggests an elevated anion gap and whether that elevation aligns with the rest of the patient’s picture.
Albumin matters because it is a major unmeasured anion. Low albumin can make the anion gap appear falsely normal or only mildly elevated. That is why many clinicians apply albumin correction to estimate a corrected anion gap. This is especially important in patients with malnutrition, inflammation, liver disease, or prolonged illness, where hypoalbuminemia can mask the degree of acidosis.
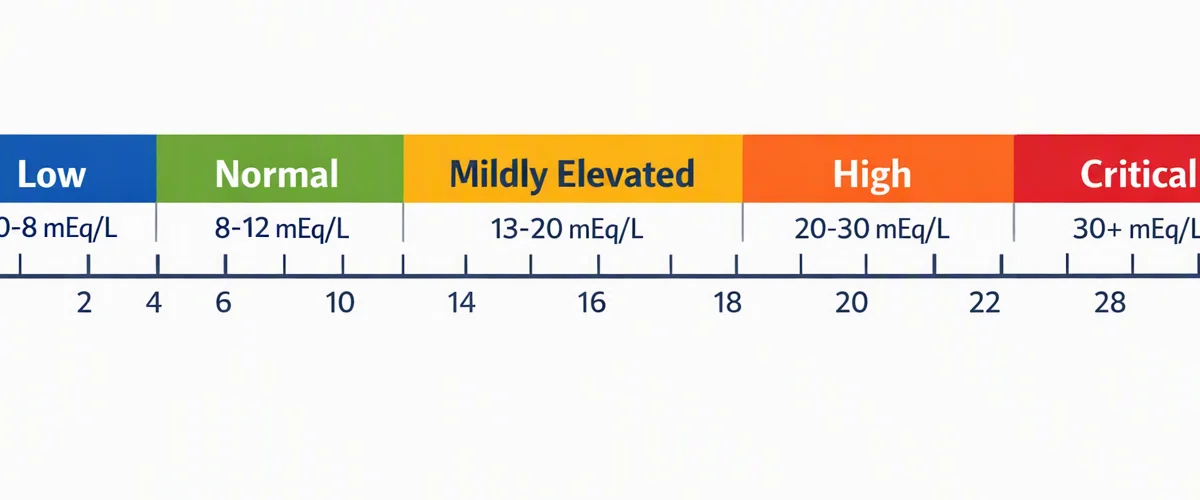
A practical stepwise approach looks like this:
- Input the available serum electrolytes into the calculator. Check whether the result indicates a high or normal gap. Check albumin and apply albumin correction if needed. Match the result with the clinical setting and other labs. Treat the number as part of broader acid-base interpretation, not as a standalone answer.
When done correctly, the calculator helps structure the workup and supports a more accurate assessment of acid-base balance. It is most useful when paired with symptoms, kidney function, ketones, lactate, and a blood gas.
Explaining High Anion Gap Findings
A high anion gap metabolic acidosis indicates that unaccounted for acids are building up. In the differential, the main categories include lactic acidosis, ketoacidosis, and toxin exposure. These processes can overlap with methylmalonic acidemia or obscure it, so interpretation should always be clinical rather than strictly formula-based.
Lactic acidosis may occur with hypoperfusion, shock, hypoxemia, seizures, or serious disease. It produces excess lactate, which raises the gap. Ketoacidosis occurs in diabetes, prolonged fasting, or starvation states, and the ketone https://anion-gap-chart074.novacrestiq.com/posts/how-to-work-out-anion-gap-in-metabolic-alkalosis bodies add to the elevated gap. Both can coexist with other metabolic abnormalities, making the final pattern harder to interpret than a single diagnosis.
Toxin exposure should also be taken into account when the gap is high. Salicylates, toxic alcohols, and other poisons may generate a substantial acid burden. In suspected ingestion, the anion gap is a helpful clue but not the endpoint. Osmolal gap testing, toxicology studies, and serial blood gas data may be needed for a complete picture.
For methylmalonic acidemia, the key point is that a high anion gap can be a sign of organic acid buildup, but not every elevated gap is caused by an organic acidemia. A systematic assessment helps separate the biochemical pattern from the underlying cause. The calculator can identify the abnormality, but interpretation requires the full context of illness severity, nutrition status, renal function, and timing of collection.
Anion Gap Correction and Clinical Setting
Initial anion gap values can be inaccurate unless the overall acid-base disorder is evaluated. This is where albumin adjustment becomes essential. Because albumin is an anion, low levels lower the baseline gap. A patient with substantial acidosis and hypoalbuminemia may therefore show a apparently normal result unless the value is corrected.
Accounting for albumin improves the utility of the anion gap calculator and makes the number more indicative of true acid burden. This is especially relevant in critically ill patients, where low albumin is common and physiologic compensation may temporarily offset pH changes. A normal pH does not rule out acidosis if compensation is present.
This is why blood gas analysis is such an important companion test. A blood gas can verify pH, bicarbonate status, and compensatory respiratory changes. Along with the corrected gap, it helps define whether the patient has primary metabolic acidosis, a superimposed respiratory process, or a complex acid-base disturbance.
Practically speaking, clinicians should avoid interpreting the anion gap in isolation. The most accurate approach integrates albumin, serum chemistry, blood gas analysis, symptoms, and time course. That complete review can distinguish an acute metabolic emergency from a chronic compensated state and can prevent under-recognition of severe disease.
Laboratory Findings in Methylmalonic Acidemia
Multiple laboratory findings help support the diagnosis of methylmalonic acidemia. The clearest is an increased level of methylmalonic acid, which indicates the underlying enzymatic block and demonstrates the presence of excess abnormal metabolites. This finding often is associated with a high anion gap state, but the magnitude of the gap can vary depending on hydration, nutrition, and concurrent illness.
Cobalamin deficiency is a key related consideration because vitamin B12 metabolism is tightly linked to methylmalonic acid handling. In some patients, low B12 or impaired cobalamin processing contributes to the biochemical picture. This is why methylmalonic acidemia and cobalamin-related disorders are often evaluated together during a laboratory assessment.
Ammonia may also be elevated, especially during decompensation. Hyperammonemia can aggravate neurologic symptoms and raise the concern for a metabolic crisis. Likewise, ketones may be present as the body shifts toward alternative fuels during stress or inadequate intake. These findings reinforce the suspicion of a serious inherited metabolic disorder.
When all these results are viewed together, the pattern stands out more clearly: elevated methylmalonic acid, possible cobalamin involvement, increased ammonia, and ketosis can accompany a high anion gap. The result is a biochemical pattern that strongly supports further metabolic testing and urgent clinical correlation.
Frequent Alternative Diagnoses
Several disorders can mimic methylmalonic acidemia on early assessment. Propionic acidemia is one of the major because it is another organic acidemia with overlapping features, including acid-base disturbance, ketosis, and an increased gap. Separating these conditions usually requires specific biochemical and genetic evaluation rather than a single electrolyte panel.
Renal failure is another common source of high anion gap acidosis. When kidney function declines, acids accumulate and unmeasured anions rise. In this setting, the anion gap may be elevated for reasons unrelated to an inborn error of metabolism, so renal markers and the overall clinical context are crucial.
Sepsis can also cause a high-gap picture through lactic acidosis, poor perfusion, and multiorgan stress. Because sepsis can present with nonspecific symptoms and rapid decompensation, it can overlap clinically with metabolic disease. A clinician evaluating a patient with suspected methylmalonic acidemia should always consider infection as a trigger or an other explanation.
More broadly, the category of inborn errors of metabolism includes many conditions that present with acidosis, hyperammonemia, and neurologic changes. Anion Gap Calculator is useful for sorting the acid-base pattern, but the differential diagnosis must remain broad until confirmatory studies narrow it down.
When the Anion Gap May Be Deceptive
Although the anion gap is useful, it is not infallible. A patient with serious disease may still show a normal anion gap if the disturbance is obscured by low albumin, early sampling, or concurrent alkalinizing processes. In methylmalonic acidemia, this can happen if the patient has received fluids, is incompletely treated, or is in a milder phase of illness.
Mixed acid-base disorders are one of the most important pitfalls. For example, a patient may have metabolic acidosis from organic acid buildup and a concurrent respiratory alkalosis from hyperventilation. The pH can look approximately normal even though the underlying disturbance is important. Blood gas interpretation is therefore essential.
Hypoalbuminemia can lower the apparent gap to the point to hide the severity of the disorder. This is why albumin correction matters so much. If albumin is low and the corrected result becomes clearly abnormal, the concern for an organic acid process rises significantly.
Laboratory variation can also affect the result. Slight differences in analyzer method, specimen handling, or repeat sampling can change the number slightly. For that reason, a single borderline value should not be read too much into. Trend data, the clinical picture, and repeat testing are often more revealing than one isolated result.
In short, the anion gap is a strong clue, not a diagnosis. The best interpretation comes from integrating the calculator output with blood gas analysis, albumin status, symptoms, and the broader biochemical pattern.
Frequently Asked Questions
How does an anion gap calculator help in methylmalonic acidemia?
An anion gap calculator helps by quickly identifying whether the patient has an elevated gap consistent with metabolic acidosis. In methylmalonic acidemia, this supports recognition of organic acid buildup and helps guide further testing. It is a useful screening tool, but it does not replace clinical evaluation or confirm the diagnosis on its own.
Which anion gap formula should be used for serum electrolytes?
The standard anion gap formula calculates with serum sodium subtracting serum chloride and serum bicarbonate. Certain formulas include potassium, but many clinical calculators omit it. The right option is the one that matches the laboratory and the clinician’s review process for serum electrolytes.
Does methylmalonic acidemia cause a normal anion gap?
Yes. Methylmalonic acidemia can at times occur with a normal anion gap, especially if there is hypoalbuminemia, early disease, treatment effects, or a mixed acid-base disorder. That is why the calculator should be paired with albumin correction and blood gas analysis.
For what reason is albumin correction important when interpreting the anion gap?
Albumin is a major unmeasured anion, so low levels can make the gap look falsely normal. Albumin correction helps estimate the true corrected anion gap and improves acid-base interpretation. This is especially important in illness, where hypoalbuminemia can mask a significant high anion gap metabolic acidosis.
What other conditions can look like methylmalonic acidemia on an anion gap test?
Common mimics include propionic acidemia, renal failure, sepsis, lactic acidosis, ketosis, and other inborn errors of metabolism. Toxin exposure can also produce a similar pattern. The anion gap is helpful for spotting the biochemical pattern, but the final diagnosis depends on the whole laboratory and clinical picture.