What the Anion Gap Measures
The anion gap is a rapid, helpful way to evaluate acid-base balance using standard electrolytes from a serum chemistry or electrolyte panel. In emergency care, it helps identify whether a patient’s metabolic acidosis is likely due to hidden acids in the blood. The calculation compares the primary measured ions, especially sodium, chloride, and bicarbonate, to estimate the presence of unmeasured ions that are not directly reported on standard laboratory values.
An Anion Gap Calculator is a valuable diagnostic tool because it turns a basic lab set into an prompt clue about the patient’s underlying metabolic disturbance. When bicarbonate is low, the calculator helps determine whether the body is losing bicarbonate or building up acid. That distinction matters in emergency evaluation because it focuses the differential diagnosis and expedites treatment decisions.
Although the anion gap is often used as a screening step, it is more than a number. It is a bedside assessment tool that supports clinical interpretation of the patient’s serum chemistry, especially when the presentation suggests shock, sepsis, toxin ingestion, kidney injury, or another acute illness. In other words, the anion gap is a connection between laboratory values and the pathophysiology behind them.
How to Apply an Anion Gap Calculator
Working with an Anion Gap Calculator is easy. Enter the patient’s sodium, chloride, and bicarbonate results from the electrolyte panel. Many calculators also request albumin because albumin has a substantial effect on the result and can alter clinical interpretation.
In the emergency department, this workflow is usually part of a broader emergency evaluation. The calculator can be used as soon as the serum chemistry is available, often while the clinician is still gathering history, physical exam findings, and additional testing. This makes it especially valuable during early bedside assessment, when a timely diagnostic tool can shape immediate next steps.
A sensible approach is:
- Review sodium, chloride, and bicarbonate together rather than in isolation. Input the values into the calculator to obtain the anion gap calculation. See whether albumin is low and apply albumin correction if needed. Evaluate the result in the context of clinical presentation, not as a standalone diagnosis.
As emergency medicine often involves incomplete information, the calculator helps structure uncertainty. A patient with altered mental status, tachypnea, or suspected toxin ingestion may have hidden acidosis before the full picture is clear. The calculator provides an immediate framework for deciding whether the problem is a high anion gap or a normal anion gap process.
Formula and Normal Range of Anion Gap
The traditional anion gap formula reads:
Anion gap = sodium - (chloride + bicarbonate)
Some laboratories include potassium, but the most common bedside version excludes it because potassium is typically minor compared with the other ions and does not meaningfully affect the result in most cases. The main concept is that the gap estimates unmeasured anions relative to measured positive ions in the serum.
The normal anion gap depends on the laboratory’s reference range, the analyzer used, and whether potassium is included. Because of this variability, clinicians should consistently interpret the number using the local reference range rather than relying on a universal cutoff. A result that seems normal in one system may be near the limit in another.
Albumin correction is essential when serum albumin is low. Albumin is a major unmeasured anion, so hypoalbuminemia can falsely lower the measured gap and hide a significant acid-base disorder. In emergency medicine, this is one of the main reasons not to stop at the uncorrected value. A corrected result may reveal a clinically important high anion gap metabolic acidosis that would otherwise be missed.
As a rule, the anion gap should be thought of as a dynamic marker rather than a fixed constant. Changes in sodium, chloride, bicarbonate, and albumin can all shift the result. This is why the calculator is valuable: it standardizes the arithmetic so the clinician can focus on clinical interpretation.
Origins of a Elevated Anion Gap
A high anion gap suggests build-up of unmeasured acids and is a hallmark feature of high anion gap metabolic acidosis. In emergency medicine, the main causes are often organized by familiar categories, but real patients may have multiple process at the same time.
Elevated lactate acidosis is a common cause, especially in sepsis, shock, hypoperfusion, seizures, or severe hypoxemia. The elevated lactate shows increased anaerobic metabolism or impaired clearance, and the anion gap can help gauge the severity of the metabolic disturbance.
Ketotic acidosis is another important cause. Diabetic ketoacidosis is the most recognized, but starvation ketoacidosis and alcohol-related ketoacidosis can also produce a large gap. In these cases, the acid load comes from ketone bodies, which are not measured directly on the electrolyte panel.
Impaired kidney function can also raise the gap because impaired excretion leads to retention of organic acids and sulfate, phosphate, and other unmeasured anions. In the emergency setting, worsening kidney function may coexist with dehydration, infection, or medication toxicity, making the acid-base disorder more complicated.
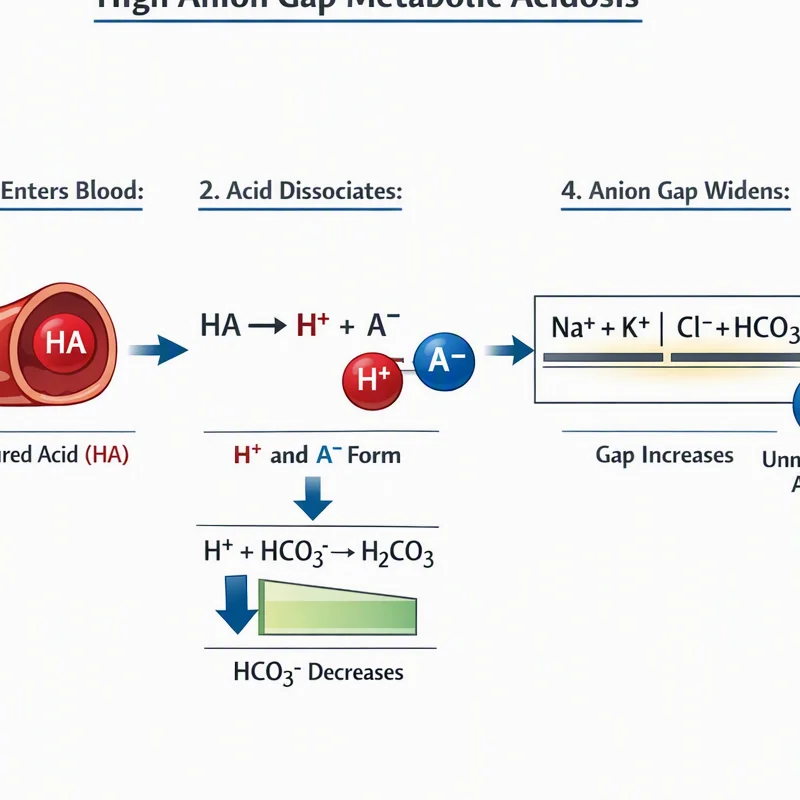
Toxic alcohols are a vital diagnosis to consider because delayed recognition can be life-threatening. Ethylene glycol and methanol can cause marked metabolic acidosis with a high anion gap, often alongside osmolar gap abnormalities. The anion gap is not specific for these exposures, but it is an important clue in toxin ingestion workups.
Other causes may include salicylate toxicity, rhabdomyolysis, and ischemic states. In practice, the anion gap is best used as part of a broad workup rather than as a single-answer test. The emergency clinician should connect the result with the patient’s symptoms, vital signs, and laboratory pattern.
Sources of a Normal Anion Gap
A standard anion gap does not exclude acidosis. It often points toward high-chloride acidosis, where bicarbonate is lost and chloride rises to preserve electroneutrality. This pattern is sometimes called non-gap metabolic acidosis.
Diarrhea is a common cause because the gastrointestinal tract can lose large amounts of bicarbonate. The body responds with a slight increase in chloride, which keeps the measured gap near normal even though acidosis is present. This is why the chloride value requires close attention when reviewing the electrolyte panel.
Tubular renal acidosis is another major cause. In this condition, the kidneys fail to acidify urine or properly handle bicarbonate, leading to ongoing or acute bicarbonate loss. Emergency clinicians may encounter it unexpectedly or during evaluation for weakness, dehydration, or unexplained metabolic disturbance.
Other mechanisms of loss of bicarbonate include pancreatic or biliary drainage, certain medications, and iatrogenic saline load. A normal gap pattern should prompt attention to volume status, medication exposure, stool losses, and kidney function. The key point is that a normal gap can still reflect true acidosis, just through a different mechanism than acid accumulation.
In the bedside workflow, this distinction helps determine whether treatment should focus on bicarbonate replacement, correcting fluid losses, or identifying a renal or gastrointestinal source.

In What Way Albumin Influences the Anion Gap
Hypoalbuminemia remains one of the most frequent reasons the anion gap can be inaccurate in emergency settings. Because albumin has a notable negative charge through protein binding, low albumin decreases the measured gap even when unmeasured acids are present. That means a patient in critical illness may have a serious acid-base disorder that looks less severe than it really is.
For this reason corrected anion gap calculations are so important. Albumin correction adjusts the raw value to account for low protein levels, which enhances detection of hidden acidosis. In practical terms, if the patient is sick enough to have low albumin, the uncorrected number should be viewed warily.
The correction does not take the place of clinical judgment. It is best understood as a fine-tuning of the anion gap calculation that increases sensitivity for metabolic acidosis in hospitalized or critically ill patients. If the corrected value rises into a high-risk range, the clinician should evaluate for lactic acidosis, ketoacidosis, renal failure, or toxin ingestion even if the initial gap seems only slightly abnormal.
Albumin correction is especially valuable when the bedside picture and the serum chemistry do not match. For example, a patient with shock, severe infection, or poor perfusion may have a deceptively normal gap because of hypoalbuminemia. In that situation, the corrected anion gap can uncover the hidden acidosis and alter the diagnostic pathway.
Urgent Care Assessment and Next Steps
In emergency medicine, the goal is not just to calculate the anion gap but to read it in a way that directs action. The number should be woven into the full picture of the patient’s acid-base disorder, symptoms, and laboratory values. That includes the arterial blood gas when appropriate, as well as the serum bicarbonate, lactate, glucose, creatinine, ketones, and toxicology testing when indicated.
A practical interpretation sequence is:
- Verify whether the result suggests high anion gap or normal anion gap physiology. Review albumin and use correction if needed. Compare the anion gap with the arterial blood gas and pH. Review lactate and other markers based on the clinical assessment. Determine whether a toxin, renal injury, or mixed disorder is present.
Lactate is particularly important because it is both a cause and a clue. If the gap is elevated and lactate is high, lactic acidosis becomes more likely, but the clinician still needs to ask why the lactate is elevated. Sepsis, hypoperfusion, medication effects, seizures, and ischemia all remain possible contributors.
Sometimes the anion gap is the first sign of an evolving problem, especially when the patient looks only mildly ill early on. In other cases, it https://anion-gap-results937.wordcanopy.com/posts/calculating-the-anion-gap-using-sodium-potassium-chloride-and-bicarbonate confirms a severe metabolic acidosis already suggested by tachypnea, altered mental status, or hypotension. The best emergency evaluation uses the calculator as a diagnostic tool that supports timely, targeted intervention.
Typical Pitfalls and Constraints
Several issues can reduce the value of the anion gap if the clinician views it too directly. A key concern is lab error. A specimen issue, contamination, or analyzer issue can alter sodium, chloride, or bicarbonate and cause a false result. If the number does not align with the clinical picture, repeat testing may be necessary.
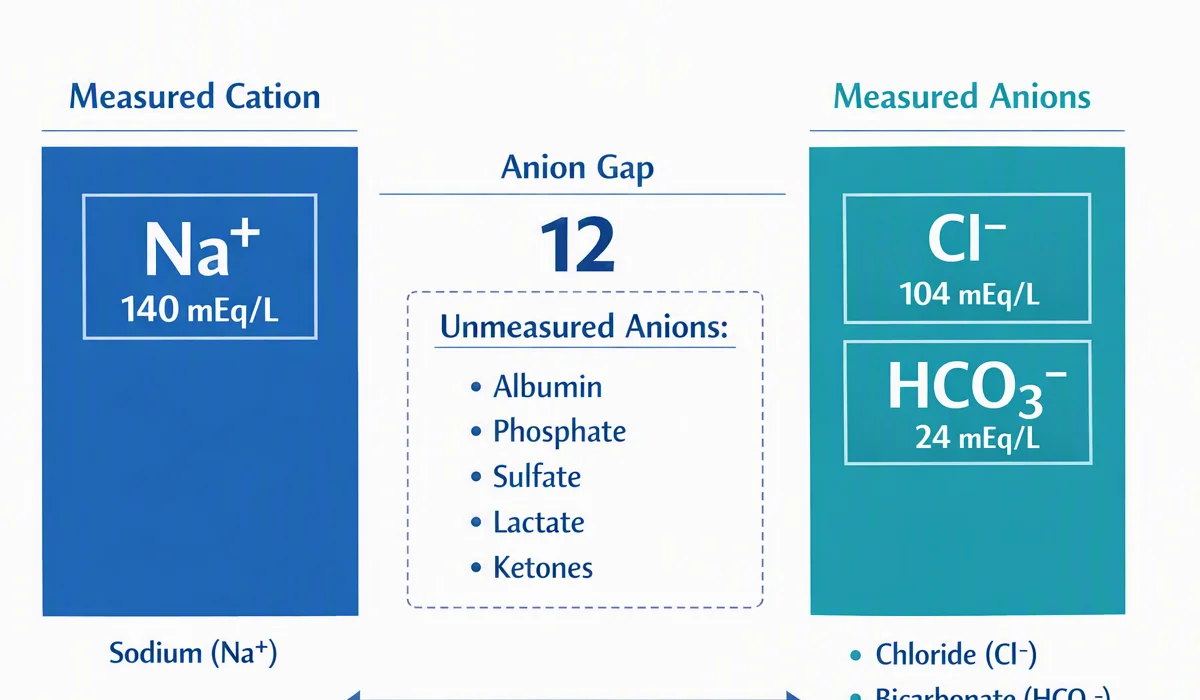
Mixed disorders are another major limitation. A patient may have high anion gap metabolic acidosis plus metabolic alkalosis, or high anion gap plus normal anion gap acidosis. In these cases, the raw number alone will not tell the whole story. This is where delta gap analysis becomes useful, because it helps identify whether the rise in the anion gap is corresponding to the drop in bicarbonate.
Pseudohyponatremia can also mislead the calculation. If sodium is falsely low because of severe hyperlipidemia or hyperproteinemia, the anion gap may look abnormal even when the acid-base picture is not straightforward. This is why the clinician should consider the broader serum chemistry context and not assume the calculator result is always exact.
Further constraints include lab-to-lab variation, changing reference range assumptions, and incomplete accounting for all unmeasured ions. The calculator is highly useful, but it is not a substitute for bedside reasoning. In emergency medicine, the strongest results come from combining the number with the presentation, the arterial blood gas, and the rest of the laboratory pattern.
Frequently Asked Questions
What is an anion gap calculator used for?
An Anion Gap Calculator is used to quickly assess the anion gap from standard electrolyte values, usually sodium, chloride, and bicarbonate. In emergency medicine, it helps identify metabolic acidosis, uncover hidden causes of illness, and guide the next diagnostic step. It is especially helpful when the clinician suspects lactic acidosis, ketoacidosis, renal failure, or toxic alcohol exposure.
What is the expected anion gap interval?
The normal anion gap is determined by the laboratory’s reference range and whether potassium is used in the formula. Because methods differ, clinicians should use the local range reported with the patient’s laboratory values. A gap that is within range in one setting may be slightly high or abnormal in another, so context matters.
How is... corrected the anion gap for albumin?
Albumin correction modifies the measured value when albumin is low, because hypoalbuminemia can hide a true gap elevation. The goal is to estimate a corrected anion gap that better represents the patient’s acid-base status. This is important in critical illness, where low albumin is common and hidden acidosis may otherwise be missed.
What causes a high anion gap in emergency medicine?
Common causes of a high gap include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols such as ethylene glycol and methanol. Other causes include salicylates, ischemia, and other forms of toxin ingestion or severe metabolic disturbance. The key is to interpret the result with the clinical picture and additional testing.
Is a normal anion gap possible with metabolic acidosis?
Yes. A normal gap can still be present in metabolic acidosis, especially in hyperchloremic acidosis caused by diarrhea, renal tubular acidosis, or other forms of bicarbonate loss. In these cases, chloride rises as bicarbonate falls, so the gap remains near normal even though the patient is acidotic.