An anion gap calculator is a useful diagnostic tool for assessing acid-base status, especially when a patient has metabolic acidosis. It helps determine whether the body has an elevated level of unmeasured anions, which can point to a particular metabolic derangement and inform clinical assessment. Used correctly, the anion gap is more than a single number: it is part of a larger interpretation that includes serum chemistry, blood gas results, and the body’s compensatory response.
This guide explains what the anion gap measures, how to calculate it, how to interpret normal anion gap versus elevated anion gap findings, and how to evaluate acid-base compensation with support from Winter's formula. It also covers albumin correction, which is important when serum albumin is low, and reviews common causes such as lactic acidosis, ketoacidosis, renal failure, and toxins.
How the Anion Gap Measures
The anion gap indicates the association between measured electrolytes in the blood, especially sodium, chloride, and bicarbonate. In plain language, it estimates the difference between the main measured cations and anions in serum chemistry. Because the body must remain electrically neutral, the gap indicates the presence of unmeasured anions when it is elevated.
In clinical practice, the anion gap is used to help classify metabolic acidosis. A high result often signals accumulation of acids that are not directly measured on a standard panel. A normal result, on the other hand, may suggest bicarbonate loss balanced by a rise in chloride. This is why the anion gap is so useful in interpretation of acid-base disorders.
The anion gap is not a direct measurement of a single substance. It is a calculated value that provides insight into electrolyte balance and hidden metabolic changes. Because the calculation depends on laboratory values, even small shifts in sodium, chloride, and bicarbonate can change the result and affect the diagnostic picture.
How to Use an Anion Gap Calculator
An anion gap calculator streamlines the arithmetic, but you still need the proper inputs. The calculator typically asks for serum sodium, serum chloride, and serum bicarbonate. Some tools also include potassium. Once those numbers are entered, the calculator provides the anion gap and may help with first-pass interpretation.
To use the tool well, enter values from the same blood draw whenever possible. Mixing values from different times can affect the calculation and reduce diagnostic accuracy. If the result is unexpectedly high or low, confirm the underlying laboratory values first. A calculator is only as accurate as the data provided.
Here is the simple workflow:
- Add the serum sodium value from the chemistry panel. Input the serum chloride value. Enter the serum bicarbonate value, also listed as total CO2. If the calculator includes it, add potassium. Examine the calculated value and compare it with the appropriate reference interval.
The best use of the calculator is not just to get a number, but to connect that number to the patient’s acid-base status. If a blood gas shows acidemia or alkalemia, the anion gap can help determine whether the process is simple or part of a mixed disorder.
Anion Gap Equation and Step-by-Step Calculation
A standard anion gap formula is written as:
Anion gap = Sodium - (Cl + HCO3)
Some practitioners also use potassium in the equation:
Anion gap = Na + Potassium - (Cl + HCO3)
The potassium-added version tends to give a marginally greater number, but most clinical references prefer the more basic formula without it. No matter which version is used, the key is uniformity in clinical assessment and analysis.
Example calculation using the standard formula:
- Serum sodium = 140 Serum chloride = 102 Serum bicarbonate = 24
Result:
140 - (102 + 24) = 14
This value must then be compared with the expected reference interval for the lab being used. Different analyzers and methods can change the normal anion gap range slightly, which is why local values matter.
The albumin level also matters because it is a major unmeasured anion. When albumin is low, the apparent anion gap may be inappropriately normal or only mildly elevated despite marked acid retention. For this reason the raw calculation is only the starting point, not the final answer.
Standard Anion Gap versus Increased Anion Gap
A typical anion gap https://anion-gap-calculation.com/calculators/corrected-anion-gap.html usually indicates that bicarbonate has been lost and replaced by chloride, producing a hyperchloremic state. This is still a form of metabolic acidosis, but it is different from the picture seen when acids accumulate and produce an high anion gap.
An elevated anion gap indicates excess undetected anions. This often reflects acids such as lactate, ketones, or toxic metabolites. In other words, the body’s measured electrolytes do not fully account for the drop in bicarbonate, so hidden acids are likely involved.
Understanding the distinction improves interpretation and helps refine the differential diagnosis. A normal gap can indicate bicarbonate loss from the gastrointestinal tract or kidneys, while an elevated gap points more strongly to acid accumulation. Both patterns can produce acidemia, but their causes and management are different.
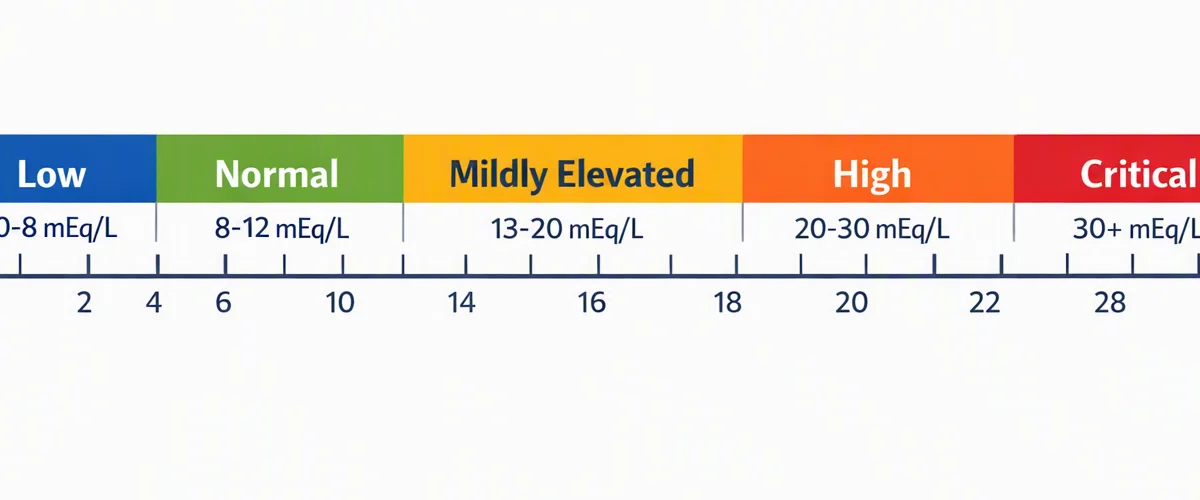
The reference range varies by lab, but a commonly used normal range is roughly 8 to 12 or 10 to 14, depending on the method. Always assess the result using the lab’s own interval, and do not rely on a single cutoff without additional context.
How to Understand Acid-Base Adjustment
Once the anion gap indicates a metabolic disorder, the next step is to check acid-base compensation. The body often compensates to metabolic acidosis with respiratory compensation, increasing ventilation to lower carbon dioxide and partly correct the pH. This is an expected compensatory response, but it has limits.
A blood gas helps show whether the primary problem is acidemia or alkalemia and whether compensation is suitable. The pH tells you the direction of the disturbance, while bicarbonate and carbon dioxide help identify the mechanism. If the pH is low and bicarbonate is low, a metabolic process is likely present. If the respiratory response is not what you anticipate, consider a mixed disorder.
Winter's formula is commonly used to estimate expected respiratory compensation in metabolic acidosis. A typical version is:
Expected pCO2 = 1.5 × bicarbonate + 8, with a range of about ±2
If the measured pCO2 falls outside the expected range, compensation may be off or another acid-base process may be present. For example, a higher-than-expected pCO2 suggests concurrent respiratory acidosis, while a lower-than-expected pCO2 suggests additional respiratory alkalosis. This step is essential for recognizing a mixed disorder.
Acid-base interpretation is strongest when the anion gap, pH, bicarbonate, and blood gas all match. The calculator provides the anionic clue, but the full pattern confirms whether the disturbance is straightforward or complex.
Adjusting the Anion Gap for Albumin
Albumin correction is needed because serum albumin is a major contributor to the anion gap. If albumin is low, the measured anion gap can underestimate the true burden of unmeasured anions. This is especially important in severely ill patients or anyone with poor nutrition, inflammation, or liver disease.
Hypoalbuminemia can make an elevated anion gap appear deceptively normal. In practice, this means a patient may have marked acidosis even though the calculator result does not look abnormal. Correcting for albumin improves diagnostic accuracy and strengthens clinical evaluation.
A commonly used adjustment applies about 2.5 mEq/L to the anion gap for each 1 g/dL albumin below 4 g/dL. This gives the albumin-corrected anion gap, which better represents the true metabolic picture. The exact correction method may vary, but the principle remains the same: low albumin decreases the measured gap.
For example, if the anion gap is 12 and serum albumin is 2 g/dL, the corrected anion gap may be roughly 17. That difference can shift interpretation from unremarkable to elevated and reveal an underlying high-gap process. In this way, albumin correction improves detection of hidden metabolic derangement.
Common Causes of High Anion Gap Metabolic Acidosis
An high anion gap in the setting of acid-base acidosis usually indicates build-up of acid from one of several major types. These causes are commonly recalled as part of a systematic differential, and the pattern can be narrowed with the blood gas, history, and other laboratory values.
Lactic acidosis occurs when lactate builds up due to tissue poor perfusion, severe infection, seizures, hypoxia, or other stress states. Because lactate is an unmeasured anion, it widens the gap and lowers bicarbonate.
Acidic ketone buildup is another classic cause. It may occur with diabetes, alcohol use, or prolonged fasting. Ketone bodies are acid-producing and generate an elevated gap that often matches worsening acidemia.
Impaired renal function can also lead to an elevated gap because the kidneys cannot excrete acid effectively. As acids accumulate, bicarbonate falls and the anion gap rises.
Toxic agents are an important and sometimes urgent cause to consider. Examples include toxic alcohols and other substances that create acid metabolites or interfere with normal metabolism. When the story does not fit a common cause, toxin exposure should remain on the list.
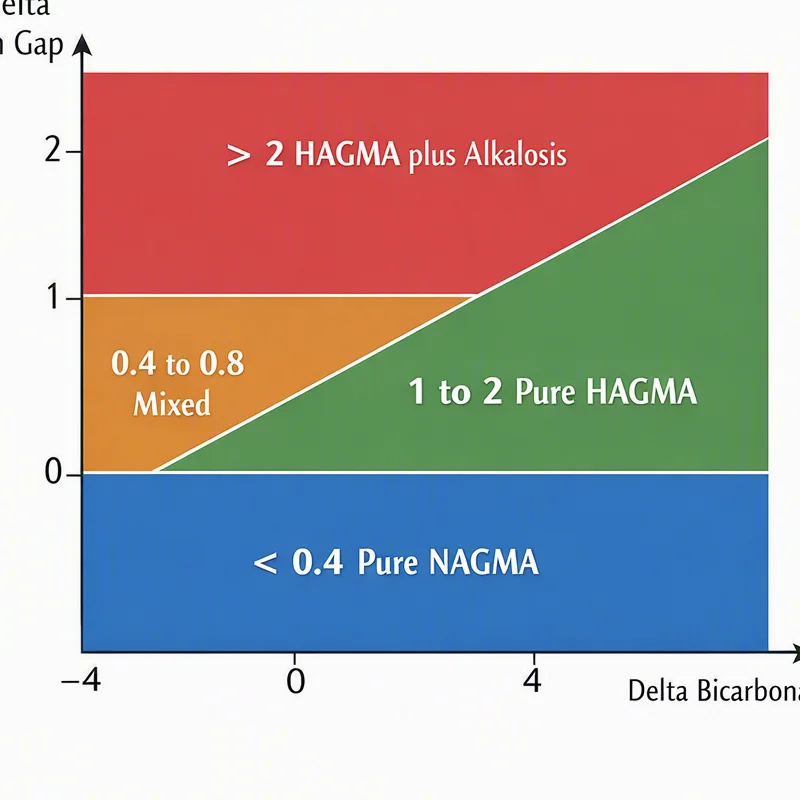
Extra clues can come from the gap difference, which compares the change in anion gap to the change in bicarbonate. This can help uncover a combined disorder, such as an elevated-gap acidosis combined with metabolic alkalosis or a concurrent normal-gap acidosis. Using the delta gap provides another layer to the interpretation and enhances better diagnostic accuracy.
In the end, the value of the calculator is not just in classifying the gap, but in linking the result to the patient’s overall acid-base picture. The combination of calculated value, blood gas, pH, and laboratory values gives the clearest view of the underlying problem.
FAQ About Anion Gap and Compensation
Why use an anion gap calculator?
An Anion Gap Calculator is used to estimate the anion gap from serum chemistry values and help evaluate acid-base problems. It is especially useful in suspected metabolic acid imbalance, where it can suggest whether excess hidden anions are present and whether further evaluation for a high-gap process is needed.
How is calculated the anion gap from lab values?
The typical anion gap formula is sodium minus chloride plus bicarbonate: serum sodium - ( serum chloride + serum bicarbonate). Certain calculations also include potassium. The value is then compared with the lab’s reference interval to determine whether it is normal or elevated.
Why does albumin correction matter when interpreting the anion gap?
Albumin correction is helpful because low serum albumin lowers the measured anion gap. In hypoalbuminemia, a patient can have a misleadingly normal number even when a significant high-gap acidosis exists. Calculating the corrected anion gap enhances interpretation and helps avoid missed diagnoses.
In what way does the anion gap help assess acid-base compensation?
The anion gap identifies whether the metabolic problem is associated with unmeasured acids, while blood gas and pH show how the body is compensating. In acid-base compensation, the lungs may lower carbon dioxide through respiratory compensation. Winter's formula helps determine whether that response is adequate or whether a different process is present.
What conditions commonly cause an elevated anion gap?
Common causes of an elevated anion gap include lactic acidosis, ketoacidosis, renal failure, and certain toxins. These conditions generate excess acids or acid metabolites, leading to metabolic acidosis with accumulation of unmeasured anions. A thorough clinical assessment should consider the patient’s symptoms, history, and laboratory values.