What the Anion Gap Calculator Does
An anion gap calculator helps estimate the difference between measured cations and anions in the blood, which is a key part of acid-base balance assessment. In real-world use, it is used to assess anion gap changes, assist with assessment of metabolic acidosis, and estimate bicarbonate deficit when serum chemistry suggests a metabolic abnormality. Because serum bicarbonate drops in many acidotic states, the calculator can help link a low bicarbonate level with the likely type of acid load and the expected compensatory response.
This is not just a simple number check. As a diagnostic tool, the calculator supports laboratory interpretation by combining electrolytes, pH, and related data to clarify whether the problem is a high anion gap metabolic acidosis or a normal anion gap metabolic acidosis. That distinction matters because it shifts the differential diagnosis, the urgency of treatment, and the broader clinical decision support approach used at the bedside.
In short, the calculator helps clinicians and students move from raw lab values to a structured view of the patient’s acid-base disorder, including possible electrolyte imbalance, respiratory compensation, and renal compensation patterns. It is especially useful when evaluating an unexplained bicarbonate level on a routine electrolyte panel or a blood gas.
How to Work Out Anion Gap and Bicarbonate Shortage
The standard anion gap formula is:
Anion gap = sodium - (chloride + bicarbonate)
Within this anion calculation, sodium serves as the main measured cation, while chloride and bicarbonate act as the measured anions. This value estimates unmeasured ions in the serum and provides insight into a possible acid load. A normal result does not exclude disease, but a clearly elevated value often indicates a high-gap process.
The bicarbonate deficit formula is used to estimate the amount of bicarbonate needed to correct a metabolic acid-base problem. In many clinical settings, bicarbonate deficit is estimated from body weight, target bicarbonate, and current bicarbonate level. The exact equation may vary by protocol, but the clinical goal is similar: determine how much alkali might be needed if bicarbonate replacement is considered. This estimate should be treated as a guide, not a stand-alone treatment plan.
Below is the practical workflow most users follow with an anion gap calculator:
- Provide sodium, chloride, and serum bicarbonate from serum chemistry or an electrolyte panel. Inspect the calculated anion gap. When albumin is low, apply albumin correction to avoid underestimating the gap. Review blood gas values to relate the result to pH and overall acid-base status. When necessary, estimate bicarbonate deficit or base deficit to guide further management.
The relationship between the numbers matters. A lower bicarbonate level with higher chloride often points toward a normal-gap process, while a low bicarbonate level with elevated unmeasured anions often suggests a high-gap process. This combination of values can reveal the underlying metabolic derangement rather than focusing on one lab in isolation.
Inputs Needed for the Calculator
To obtain a meaningful value, the calculator relies on accurate electrolytes and associated clinical data. The core inputs are usually sodium, chloride, and bicarbonate, but many versions also include potassium and albumin. Potassium may be included in some formulas because it can slightly change the calculated gap, though many standard approaches omit it for simplicity.
A blood gas or arterial blood gas adds valuable context. These values help confirm the presence of acidemia or alkalemia and show whether the serum bicarbonate aligns with the observed pH. A blood gas can also help identify whether the lungs are contributing through respiratory compensation or whether the pattern is primarily renal in origin.
Albumin deserves special attention because it affects the expected baseline anion gap. When albumin is low, the measured gap can look falsely normal, which is why albumin and albumin correction are important inputs or adjustments in many calculators. Without them, a clinically important metabolic acidosis may be missed.
Common data elements used in this kind of calculator include:
- Sodium from the electrolyte panel Chloride from serum chemistry Potassium, when the calculator includes it Albumin for correction of the anion gap Blood gas or arterial blood gas values for acid-base context pH to define acidemia or alkalemia
Accurate input data enhances laboratory interpretation. If the numbers are outdated, contaminated, or drawn during rapid fluid shifts, the output may not reflect the current metabolic state. In critical care and emergency medicine, the timing of sample collection can be as important as the equation itself.
Interpreting the Results
Reading the output starts with the magnitude of the anion gap. A high anion gap usually means excess unmeasured anions are present, often due to organic acids or impaired clearance. A https://anion-gap-tracker398.urbanvellum.com/posts/anion-gap-calculator-with-albumin-correction-2 normal anion gap suggests bicarbonate loss or chloride gain rather than accumulation of unmeasured acids. Each pattern represent a form of acid-base disorder, but they point in different diagnostic directions.
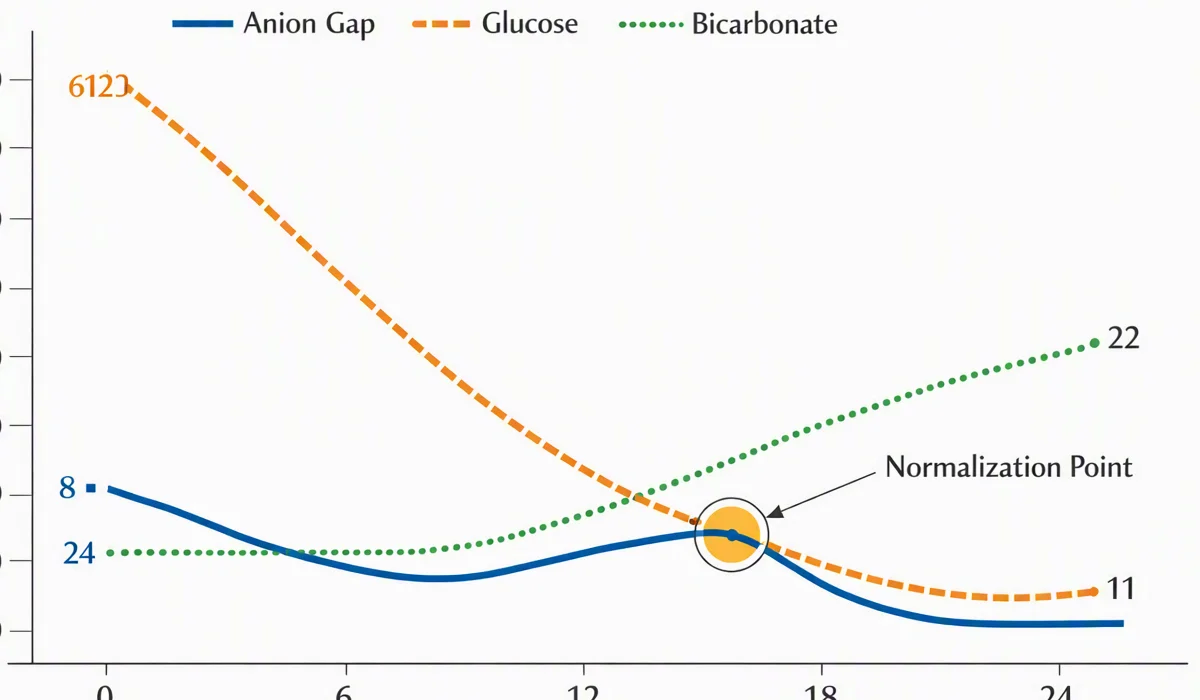
Combine the anion gap with the pH from a blood gas. If the pH is low and bicarbonate is low, metabolic acidosis is likely. If the pH is near normal, there may still be a mixed disorder or a compensatory response masking the severity of the process. That is why laboratory interpretation should include bicarbonate, gap, and pH together rather than relying on one value alone.
A useful way to think about the result is:
- Increased anion gap: consider accumulation of acids and assess high-gap causes. Standard anion gap: consider bicarbonate loss or hyperchloremic states. Unexpectedly normal result: consider low albumin, lab variation, or mixed disorders.
The presence of respiratory compensation does not erase the primary metabolic problem. A patient may have low bicarbonate and a near-normal pH because ventilation has changed in response to the acid load. Likewise, renal compensation may take time, so an acute metabolic derangement can look different from a chronic one. These patterns are part of the larger clinical picture and help determine whether the change is acute, chronic, or mixed.
Main Causes of Reduced Bicarbonate
A bicarbonate deficit commonly develops when the body consumes bicarbonate or uses it up while neutralizing excess acid. One of the most common causes is lactate-driven acidosis, in which elevated lactate indicates tissue hypoperfusion, hypoxia, or severe metabolic stress. The result is a high acid load and a declining bicarbonate level as the buffer system strives to maintain pH.
Ketone acidosis is an additional frequent cause. In diabetic, alcoholic, or starvation states, ketone production surges and consumes bicarbonate. This often produces a raised anion gap acidosis with low serum bicarbonate and a low pH. The combination is especially important in emergency medicine because delayed recognition can lead to fast decline.
Renal failure can cause bicarbonate deficit through reduced acid excretion and impaired regeneration of bicarbonate. When kidneys cannot effectively clear acids, the result may be a high-gap pattern, a normal-gap pattern, or a mixed disorder depending on the stage and the accompanying organ dysfunction. Renal compensation is limited when kidney injury is severe.
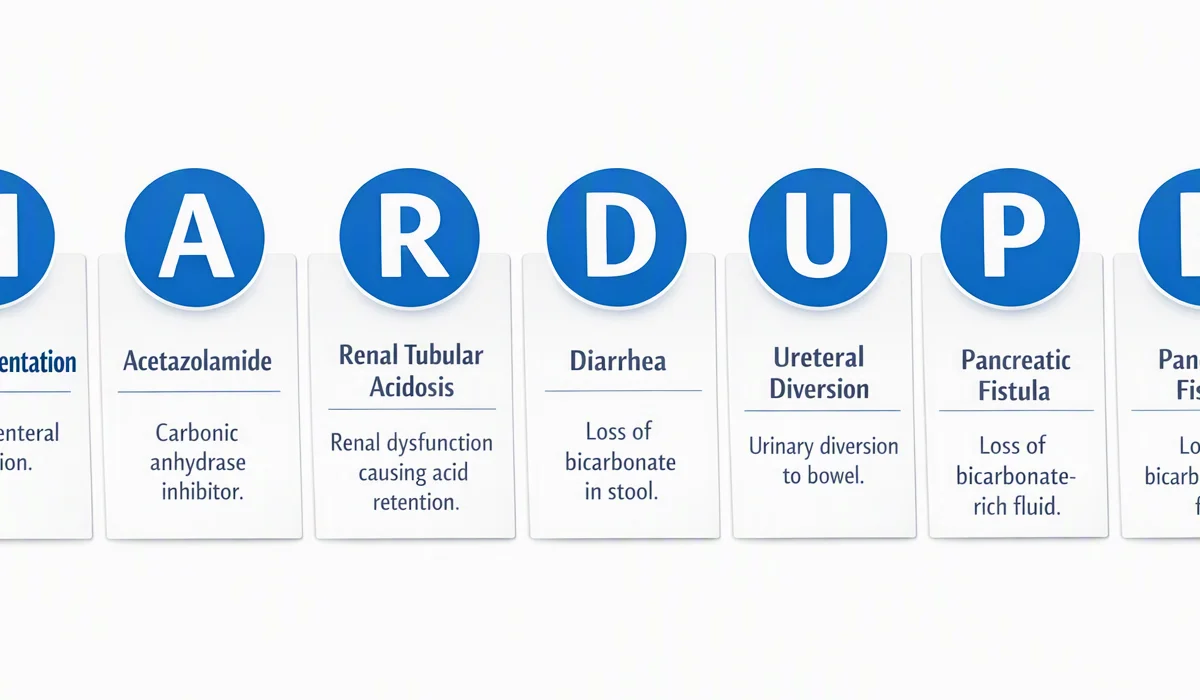
Bowel loss is a classic cause of normal-gap metabolic acidosis. Gastrointestinal bicarbonate loss lowers serum bicarbonate without creating the same unmeasured anion accumulation seen in high-gap states. Chloride often rises in compensation, so the electrolyte imbalance may look hyperchloremic.
Other contributors to bicarbonate deficit can include medication effects, toxin exposure, and combined metabolic derangements. Because these processes overlap, a single calculator result should always be integrated with the clinical setting, symptoms, and full serum chemistry profile.
Correcting for Albumin and Additional Factors
Albumin correction is crucial when the measured anion gap seems lower than expected. Albumin is a primary unmeasured anion, so when it declines, the gap may appear normal even though substantial acid accumulation is present. Using a adjusted anion gap can identify hidden metabolic acidosis and refine acid-base balance assessment.
In practical terms, low albumin can obscure the severity of a metabolic abnormality. That is why clinicians often correct the anion gap before assuming that the gap is normal. The corrected value is not just an academic adjustment; it can change the differential diagnosis and influence treatment decisions.
Additional factors can influence interpretation too:
- Potassium may modestly shift the calculation in some formulas. Significant changes in sodium or chloride can distort the apparent gap. Acid-base status may be combined, with both respiratory and metabolic components. Changes in albumin, lactate, or renal function can confound the picture.
The key point is that the raw number is only one part of the story. A corrected result more accurately shows the patient’s true buffer system status and the probable burden of acid load. This makes the calculator more accurate as a clinical decision support aid.
Medical Use Cases and Limitations
In acute care, the calculator helps swiftly screen for dangerous metabolic abnormalities such as lactate-related acidosis, ketoacidosis, or toxin-related acidemia. In intensive care, it supports ongoing monitoring of organ dysfunction, fluid shifts, and changing acid-base balance during ICU treatment. In both settings, it can assist choose the next action in workup or resuscitation.
Still, there are important diagnostic limitations. The calculator does not reveal the exact cause of the disorder by itself. It also cannot take the place of clinical assessment, imaging, or broader laboratory interpretation. Mixed disorders are common, and a patient may have simultaneous respiratory compensation, renal compensation, and another metabolic process that masks the expected pattern.
Other limitations include:
- Dependence on accurate and timely serum chemistry values Reduced reliability when albumin is not considered Potential confusion in mixed or chronic acid-base disorders Variation between formulas used for bicarbonate deficit or base deficit
A practical approach is to use the calculator as a structured diagnostic tool rather than a final answer. It is most valuable when combined with the arterial blood gas, clinical context, and serial lab trends. That broader workflow helps clarify whether the problem is acute, chronic, or a combination of metabolic and respiratory changes.
Frequently Asked Questions
How is defined the anion gap and what makes it significant?
The anion gap is a computed value that estimates unmeasured ions in the blood. It is important because it helps identify metabolic acidosis and determine if the patient has a high anion gap metabolic acidosis or a normal anion gap metabolic acidosis. That separation refines the differential diagnosis and informs the next steps in evaluation.
How is bicarbonate deficit from lab results?
Bicarbonate deficit is calculated by comparing the patient’s current serum bicarbonate with a target bicarbonate level and including body size or distribution volume. The exact formula depends on the protocol being used, but the goal is to estimate the amount of bicarbonate replacement that might be needed. This estimate should always be interpreted in conjunction with the blood gas and the overall acid-base disorder.
What causes a high anion gap metabolic acidosis?
Common causes include lactate accumulation from lactic acidosis, ketoacidosis, and renal failure. Other causes can include toxins and severe metabolic derangements. A high gap indicates unmeasured anions are building up, which usually means there is an excess acid load or impaired acid clearance.
Why do you correct the anion gap for albumin?
You correct the anion gap for albumin because low albumin can make the measured gap look falsely normal. Albumin correction helps reveal a more accurate corrected anion gap, which improves detection of hidden metabolic acidosis. This is especially important when the clinical picture suggests acid-base balance is disturbed but the raw number seems reassuring.
When is bicarbonate replacement considered?
Bicarbonate replacement may be considered when there is significant acidemia, a substantial bicarbonate deficit, or a specific clinical situation where buffering is needed while the underlying cause is treated. It is not used automatically for every acidosis, because the best management often focuses on the underlying disorder such as lactic acidosis, ketoacidosis, renal failure, or diarrhea. The decision should be based on the full blood gas, electrolyte panel, and clinical context.