What exactly is the Anion Gap?
The anion gap is a straightforward approach to approximate whether there are unseen ions in the blood. It is calculated from common values on the electrolyte panel and helps you interpret an acid-base disorder, especially metabolic acidosis. For future doctors, the anion gap is one of the quickest methods to move from raw serum electrolytes to a useful clinical interpretation.
In practice, the anion gap reflects the balance between measured sodium, chloride, and bicarbonate. Since the body must maintain electrical neutrality, a change in one of these values often indicates an accompanying electrolyte imbalance or a hidden metabolic derangement. That is why the anion gap is such a useful diagnostic tool in patient evaluation.
Students often think of it as a memorized number, but it is far more helpful as a clue. A high anion gap suggests that acid is accumulating or that unmeasured anions are present. A normal anion gap suggests a different set of causes, often involving bicarbonate loss with compensatory chloride retention. Understanding this distinction is crucial for building a strong differential diagnosis.
How to Use an Anion Gap Calculator
An anion gap calculator is a convenient way to carry out the gap calculation efficiently during study sessions, rounds, or exam review. Most calculators require serum sodium, serum chloride, and serum bicarbonate. After entering those laboratory values, the calculator provides the anion gap, at times with a corrected result if albumin is low.
The process is simple:
- Enter the patient’s sodium value. Input the chloride value. Enter the bicarbonate value. Inspect the calculated anion gap and compare it to the reference range.
Clinically, the calculator helps direct attention on the bigger question: does the acid-base picture fit metabolic acidosis, and if so, what is the underlying cause? A calculator is helpful because it removes arithmetic errors and streamlines recognition of patterns in the electrolyte panel.
For exam settings, always combine the calculator output with the full context of the patient’s acid-base status. A single number does not confirm the diagnosis. Instead, it guides the next step in the patient evaluation, whether that means checking lactate, ketones, kidney function, or medication exposure.
Anion Gap Formula and Typical Range
The traditional anion gap formula is:
Anion gap = sodium - (chloride + bicarbonate)
This formula uses the usual measured cations and anions on a standard panel. Since sodium is often the dominant cation, the result estimates the difference between measured positive and negative charges. The precise formula may vary slightly depending on the lab or calculator, but this version is the best known for medical students.
The normal anion gap depends on the lab method and whether potassium is included. Many teaching resources use a reference range approximately 8 to 12 mEq/L without potassium, but you should always rely on the site-based reference range when available. The important point is not memorizing one universal number, but recognizing whether the value is elevated relative to the expected range.
Albumin matters because it is a major unmeasured anion. When albumin is normal, the gap better reflects the expected balance of measured and unmeasured ions. When albumin is low, the gap may appear falsely reassuring. That is why albumin correction is an key part of interpretation, especially when you suspect metabolic acidosis but the raw number looks normal.
A helpful exam habit is to think in layers: first calculate the gap, then decide whether it is normal or elevated, and then use the pattern to narrow the differential diagnosis. This structured approach improves confidence and reduces missed diagnoses.
Modified Anion Gap for Low Albumin
Hypoalbuminemia lowers the calculated anion gap because albumin provides negative ion charge to the blood plasma. If albumin is reduced, the patient may still have meaningful acidosis even though the uncorrected gap looks normal. That is why the corrected anion gap is so important in real-world medicine.
The idea behind the correction is simple: if albumin is low, the gap should be adjusted upward to account for the missing unmeasured anions. This albumin correction helps prevent underestimating a hidden high anion gap process. For students, this is a frequent test pitfall and a common source of error during clinical interpretation.
A practical way to think about it is this: the more decreased the albumin, the more likely the uncorrected value will minimize acid burden. In critically ill patients, patients with malnutrition, liver disease, or inflammation, checking for hypoalbuminemia should be part of the normal assessment. If the calculator includes corrected output, use it. If not, calculate it manually or use caution.
Remember that the corrected result does not replace the rest of the evaluation. It simply increases sensitivity for detecting hidden acid-base status changes. In other words, the corrected number helps you ask better questions about the patient’s metabolic state rather than stopping at the first result.
High Anion Gap Metabolic Acidosis: Common Causes
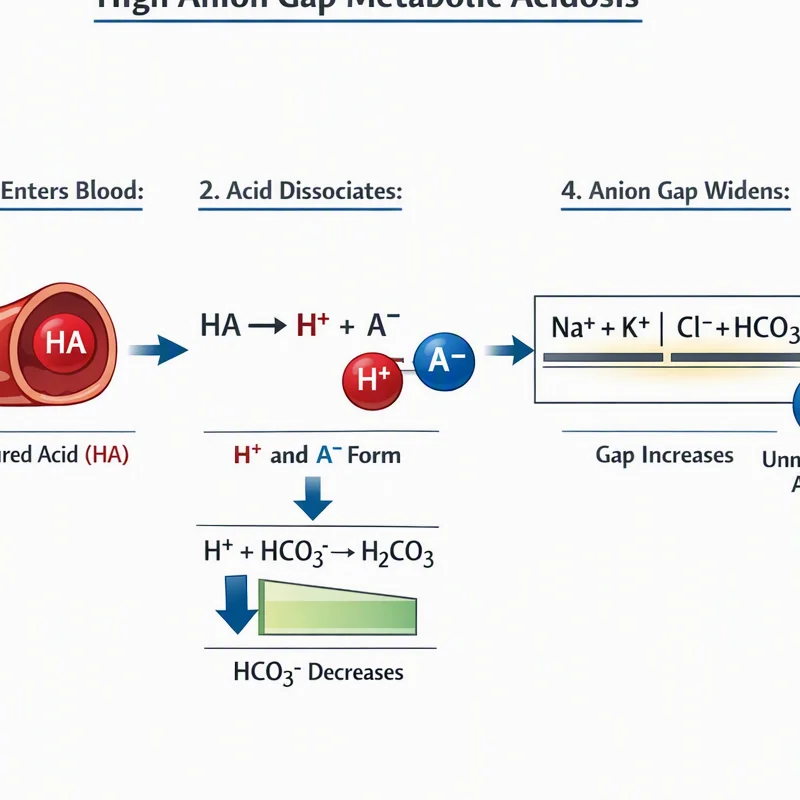
A high anion gap generally indicates there are excess acids in the blood or an accumulation of unmeasured anions. This pattern is important for diagnosing high anion gap acidosis and is one of the most commonly examined topics in acid-base review. The leading causes medical students should know include lactic acidosis, ketoacidosis, and uremia.
Lactic acidosis develops when lactate builds up due to tissue hypoperfusion, hypoxia, sepsis, seizures, or severe metabolic stress. It is a well-known cause of elevated gap and should be considered whenever the patient appears ill. In practice, lactate is often one of the initial follow-up labs when a gap is high.
Ketoacidosis is an additional major cause. This includes diabetic ketoacidosis, alcoholic ketoacidosis, and starvation ketosis. The shared theme is ketone body accumulation, which contributes unmeasured anions and raises the gap. Look for hyperglycemia, dehydration, abdominal pain, or a compatible history, depending on the scenario.
Uremia from advanced kidney dysfunction can also produce a high anion gap because retained acids are not adequately excreted. In this setting, kidney function testing and the overall clinical picture are essential. A student should always connect the laboratory result to the patient’s symptoms, renal history, and broader metabolic picture.
Other causes may appear on exams, but these three are the fundamental starting points. A useful strategy is to ask: is the body producing extra acid, failing to clear acid, or both? That question quickly organizes the differential diagnosis and prevents random memorization.
Normal Anion Gap Metabolic Acidosis: Common Causes
A normal anion gap metabolic acidosis is referred to as hyperchloremic acidosis. With this pattern, bicarbonate is depleted, and chloride rises to preserve electrical neutrality. The result is a normal measured gap even though the patient is clearly acidotic. This is a classic example of why looking only at the gap can be misleading.
Diarrhea is one of the frequent causes. The gastrointestinal tract loses bicarbonate-rich fluid, and the serum chloride increases in compensation. If a patient has significant GI losses and a low bicarbonate, a normal gap should make this diagnosis move higher on the list.
Renal tubular acidosis is another important cause. Here, the kidneys fail to acidify the urine or conserve bicarbonate properly. It is a key consideration when the patient has persistent metabolic acidosis without obvious GI losses, especially when kidney function seems otherwise preserved.
These patterns matter because the treatment depends on the mechanism. If the cause is hyperchloremic acidosis, the approach may focus on fluid loss, renal evaluation, or replacing bicarbonate in selected cases. The gap itself does not determine the treatment; it guides the workup and sharpens the differential diagnosis.
For students, the most important takeaway is that a normal gap does not mean “no problem.” It often means the acid-base disorder is caused by bicarbonate loss rather than unmeasured acid accumulation. That distinction is vital for accurate interpretation.
Clinical Assessment Guidelines for Future Clinicians
Careful clinical assessment begins with the full electrolyte panel, not just the number from the tool. First, establish there is an acid-base disorder by looking at pH and bicarbonate. Next, determine the gap. Then, judge whether the pattern matches a high anion gap or a normal anion gap state. Step four is to match the result to the most likely cause.
A useful mental framework is to focus on the leading underlying cause before chasing rare diagnoses. If the patient is unstable, suspect lactic acidosis. If there is diabetes, poor intake, or alcohol use, think about ketoacidosis. If kidney function is poor, suspect uremia. If there is diarrhea or chronic GI loss, move toward diarrhea and renal tubular acidosis.
A frequent exam pitfall is ignoring hypoalbuminemia. If albumin is low, the raw gap may mask the degree of acidosis. This is why corrected values are part of good practice and why many acid-base disorders questions include albumin for a reason.
Here are a few quick habits that help in patient evaluation:
- Always review the full electrolyte panel, not just the anion gap. Verify whether the result aligns with the patient’s acid-base status. Use albumin correction when albumin is abnormal. Use the gap to sharpen the differential diagnosis, instead of finish it. Consider whether the pattern suggests a metabolic derangement or compensation for another disorder.
In exam settings, practice turning a raw number into a story. Example: “This patient has metabolic acidosis with an elevated gap, which raises concern for lactic acidosis, ketoacidosis, or uremia.” This kind of reasoning is exactly what faculty expect when they assess understanding of the anion gap calculator and its clinical use.

FAQ About the Anion Gap Calculator
What is an anion gap calculator used for?
An anion gap calculator is used to efficiently calculate the anion gap from sodium, chloride, and bicarbonate. It aids in identifying whether a patient’s metabolic acidosis is more in line with a high anion gap state or a normal anion gap state. For medical students, it is a practical diagnostic tool for organizing the differential diagnosis.
What is the normal anion gap range?
The normal anion gap changes by lab and method, so the exact reference range may vary. Many educational settings use a range around 8 to 12 mEq/L without potassium, but you should always assess the result in the context of the local laboratory values. The key is whether the result is not typical for that specific setting and whether the patient’s acid-base status matches the pattern.
Why do you correct the anion gap for albumin?
You modify the anion gap for albumin because hypoalbuminemia can https://anion-gap-results937.wordcanopy.com/posts/what-does-it-mean-if-an-anion-gap-of-20-mean make the uncorrected value look lower than it truly is. Since albumin is a major unmeasured anion, low levels can mask a clinically important high anion gap disorder. The corrected anion gap refines interpretation and helps prevent overlooking a significant metabolic problem.
What causes a high anion gap metabolic acidosis?
The most common causes of high anion gap metabolic acidosis include lactic acidosis, ketoacidosis, and uremia. These conditions increase unmeasured acids or reduce acid clearance. When the gap is elevated, the next step is to find the underlying cause based on the clinical picture, history, and other laboratory findings.
What can cause a typical anion gap metabolic acidosis?
A normal anion-gap metabolic acidosis is commonly caused by diarrhea, renal tubular acidosis, and other forms of chloride-rich acidosis. In such situations, bicarbonate is depleted or depleted and chloride rises to maintain balance. This pattern is clinically important because it indicates the absence of excess unmeasured acids and toward the possibility of bicarbonate loss or renal handling problems.